
By 2024, regulatory bodies like the FDA and TGA began classifying advanced photobiomodulation devices as Class II medical equipment, rendering generic wavelength advice outdated.
Led light therapy how does it work comes down to photons stimulating mitochondrial cytochrome c oxidase to increase cellular ATP production. Red light at 660 nm penetrates superficial tissue, while near-infrared light at 850 nm reaches deeper muscle. This photochemical reaction drives measurable biological responses without generating heat.
Understanding this biophysics separates effective devices from decorative lights. You will learn how irradiance, optical lens design, and wavelength ratios determine whether a panel or facial mask delivers actual therapeutic doses.
A clinical scenario that reveals how LED light therapy actually works

An aesthetician treating chronic facial inflammation with a multi-wavelength device does not rely on heat. During a 15-minute session, photons from the LEDs pass through the epidermis without raising tissue temperature. This separates photobiomodulation (PBM) from lasers or intense pulsed light devices, which intentionally damage tissue through thermal injury to trigger healing.
Understanding led light therapy how does it work requires looking past marketing claims and into the physics of light-tissue interaction. Kevin Zhang, Chief Technology Officer at REDDOT LED, has spent over 15 years in optical engineering and PBM manufacturing. His perspective is clear: the mechanism depends entirely on specific wavelengths acting as keys that fit into cellular photoreceptors. The primary target is cytochrome c oxidase, an enzyme within the mitochondria. When photons of the correct wavelength strike this enzyme, they trigger a cascade of biological responses.
To evaluate whether a device actually engages this mechanism, buyers should verify five physical parameters before trusting any clinical promise:
- Confirm the peak wavelength matches published action spectra for cytochrome c oxidase.
- Verify the irradiance level delivers enough photons per square centimeter to reach the target tissue depth.
- Check that the device operates without generating measurable surface heat.
- Ensure the emission spectrum is narrow rather than broad-spectrum white light.
- Request third-party spectral test reports rather than relying solely on manufacturer spec sheets.
The biophysics are exacting. Light must arrive at the right wavelength, with sufficient density, without thermal interference. This precision explains why understanding the underlying physics matters more than memorizing advertised benefits.
The biophysics of photobiomodulation explained
A 10nm deviation in peak wavelength can shift absorption away from the optimal action spectrum of cytochrome c oxidase, rendering the light biologically inert. That single specification separates medical-grade hardware from decorative electronics.
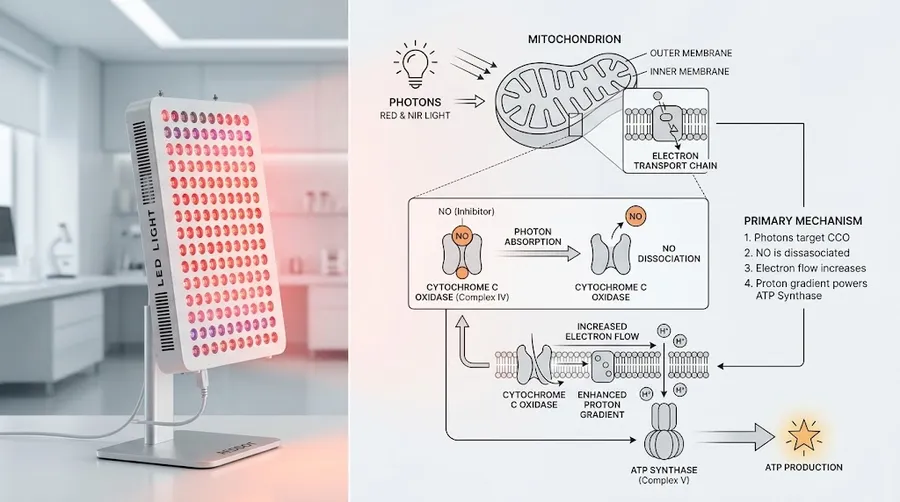
Research published in Photobiomodulation, Photomedicine, and Laser Surgery establishes that red and near-infrared photons are absorbed by mitochondrial chromophores. Once absorbed, three downstream events occur. Adenosine triphosphate (ATP) production increases, giving cells more energy. Nitric oxide releases transiently, improving local blood flow. Reactive oxygen species modulate and contribute to cellular signaling without necessarily causing oxidative stress.
Does LED light therapy for skin really work? The answer depends on distinguishing between thermal light sources and non-thermal PBM. Therapeutic effects rely entirely on photochemical reactions. Tissue heating plays no part. Wavelength dictates the depth of penetration, while photon density dictates the strength of the cellular response. This framework governs all effective treatments.
Why wavelength precision is non-negotiable for cellular response
Manufacturing under ISO 13485:2016 guarantees that LEDs emit the exact wavelengths claimed in clinical literature. Cheap consumer electronics often exhibit batch-to-batch variability that destroys dosimetric accuracy. Multi-wavelength engineering solves this when executed correctly. REDDOT LED’s E49 7 Color LED Facial Mask uses 193pcs LEDs across Red, Blue, Green, Yellow, Purple, Cyanine, and White(Laser) to target different chromophores safely at 5V/1A for home use. Each color addresses a distinct biological pathway, requiring strict binning during assembly.
Optical precision determines whether photons trigger chemistry or merely illuminate skin.
Why irradiance and optics dictate biological efficacy
Moving a light source just two inches further from the skin drastically reduces the effective dose due to inverse-square law drop-off. Distance destroys dosage faster than almost any other variable in PBM application.
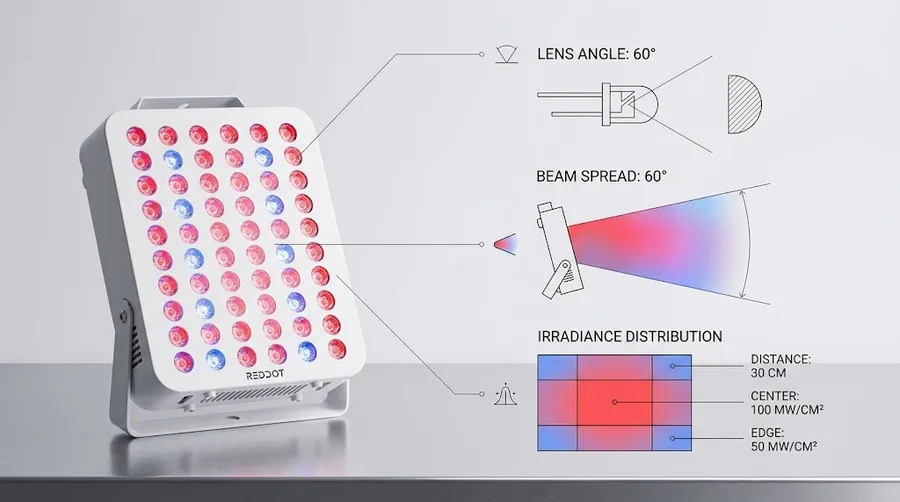
Irradiance, measured in mW/cm², determines whether a device delivers a therapeutic dose or simply shines light. The World Association for Photobiomodulation Therapy (WALT) dosimetry guidelines establish globally recognized thresholds for irradiance and treatment duration. Falling below these thresholds yields zero biological effect.
REDDOT’s EST-X2 Therapy Lamp illustrates applied optical engineering. It delivers >200mW/cm² irradiance at 6 inches using 60 X5W LEDs. Interchangeable 30-degree and 60-degree lens options allow practitioners to control light coverage based on the treatment area. Research in Lasers in Medical Science documents a biphasic dose response: too little irradiance yields no result, while excessive irradiance inhibits cellular function. Precise optical engineering prevents both extremes.
How lens geometry transforms raw LED output
Raw LEDs emit light at approximately 120 degrees. Secondary optics like 30-degree or 60-degree lenses focus that emission into usable therapeutic delivery. Improper lens selection causes rapid intensity loss over short distances. REDDOT’s 17-member R&D team holds 70+ granted patents focused heavily on these optical geometries. Devices exported to more than 80 countries require this consistency to deliver predictable clinical outcomes.
One hardware upgrade illustrates how seriously optical safety must be taken. Existing LED panel jumpers previously had insulation only on the front and back sides, leaving metal exposed laterally. Under high voltage differentials, this punctured the insulating varnish on circuit boards, causing short circuits that burned out LED chips. Upgrading to fully insulated jumpers eliminated this hazard entirely. The slight cost increase per unit prevents catastrophic after-sales failures and protects brand reputation.
Optics dictate whether engineering translates into biology.
The science of wavelength ratios in device engineering
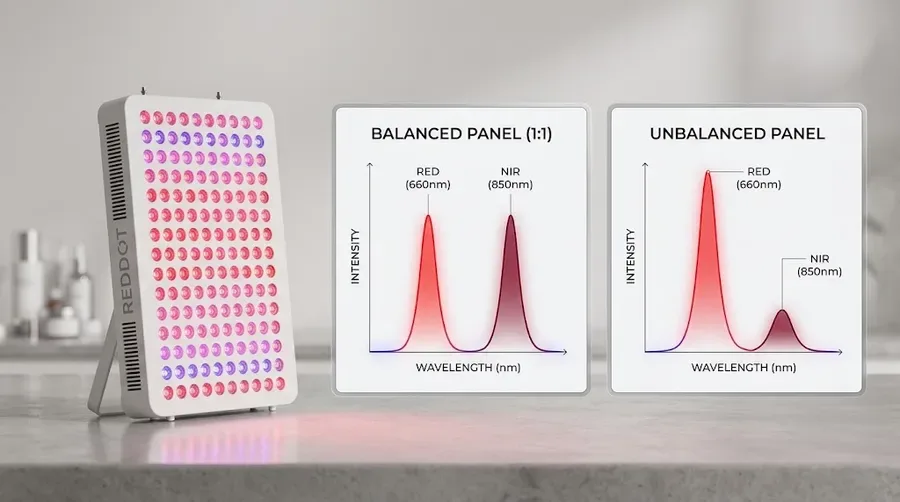
Single-wavelength biology explains the mechanism. Multi-wavelength engineering makes it practical. Combining red and near-infrared light produces synergistic effects because each targets different tissue depths. A strict 660nm:850nm ratio is considered optimal. The 660nm wavelength targets superficial tissue and skin health. The 850nm wavelength penetrates deeper into muscle and joint structures.
REDDOT’s T1 Desktop Panel applies this principle directly. Its 120pcs x1W LEDs maintain a strict 660nm:850nm=1:1 wavelength ratio. This delivers balanced, close-range photobiomodulation without over-saturating one tissue depth. Generic market panels frequently use arbitrary LED counts, such as 3:1 or 5:1 ratios, dictated by component availability rather than biological rationale. The resulting dosage delivery becomes unpredictable.
Translating cellular theory into reliable hardware
Driving mixed-wavelength LEDs on the same circuit board presents an electrical challenge. Red and near-infrared diodes have different forward voltage requirements. Maintaining a true 1:1 ratio requires independent current regulation for each wavelength bank. REDDOT enforces this standard across its OEM and ODM development processes.
Evaluating LED light therapy benefits requires verifying how manufacturers handle these electrical realities. Buyers assessing new suppliers should confirm four engineering standards:
- Independent current drivers exist for each wavelength bank.
- Spectral test reports verify the actual emitted ratio matches the advertised ratio.
- Thermal management systems prevent wavelength drift during extended operation.
- Forward voltage matching is documented for all diode batches.
Electrical architecture determines whether a stated ratio actually reaches the patient.
How different mechanisms require different optical outputs

How LED light therapy works changes fundamentally depending on the anatomical target. Full-body systemic recovery requires high irradiance, broad beam angles, and deep-penetrating near-infrared light. Localized mucosal treatments demand low irradiance, narrow targeting, and specific visible wavelengths. One set of parameters cannot serve both applications.
REDDOT’s Rhinitis Lamp demonstrates specialized engineering. Its 650nm wavelength delivers a precisely controlled 10mW/cm² irradiance via 12x3W LEDs. The 8x2cm compact size enables localized intranasal application rather than broad skin exposure. For professional clinic settings bridging targeted facial care and stable power delivery, higher voltage architectures support consistent multi-wavelength output. The RD7 7 Color LED Facial Mask operates at DC24V 2A with 193pcs LEDs, providing the electrical stability required for continuous professional use.
Adapting the PBM framework for specific use cases
Sports recovery brands require different optical specifications compared to veterinary equipment manufacturers or skincare companies. REDDOT provides OEM and ODM support covering concept design, prototype engineering, and certification assistance. This helps ensure that optical output matches the specific biological mechanism required by the end-user.
There is some evidence these therapies work, but it is far from conclusive if the device parameters do not align with the specific tissue depth and chromophore being targeted. What are the negatives of LED light therapy? The primary risk is applying the wrong dosage to the wrong tissue. Buyers developing new product lines should follow this alignment process:
- Identify the exact tissue depth and target chromophore for the intended condition.
- Select wavelengths proven to reach that depth without scattering.
- Calculate the required irradiance to achieve a therapeutic dose within a practical time window.
- Design secondary optics to maintain that irradiance at the intended working distance.
Matching the optical output to the biological target is the final requirement for efficacy.
Bridging the gap between safety standards and therapeutic performance
People often ask “What are the negatives of LED light therapy?” and expect answers about biological side effects. The real risks usually originate on the factory floor. Poor manufacturing leads to electrical hazards, inconsistent dosing, or devices that simply fail to deliver photons at the promised irradiance. A multi-wavelength facial mask running 193 LEDs across seven wavelengths requires stable power delivery; without it, wavelength accuracy drifts and the intended cellular response never happens.
The International Electrotechnical Commission (IEC) 60601-1 standard dictates essential performance and electrical safety for any device intended for medical or therapeutic use on human tissue. This standard governs how internal components handle voltage spikes, thermal loads, and physical stress over thousands of hours. Seemingly minor component choices dictate overall reliability. During production runs of the RDPRO-300 model, engineers identified two assembly issues. The control board’s ribbon cable overlapped with the power supply, creating a hazard where wire insulation could wear down.
Screws used to secure the shell were 36mm long, pressing against the control board when tightened and causing the screen to go black. The engineering team redesigned the control board mounting position to create clearance and updated the Bill of Materials to specify 34mm screws. That 2mm difference eliminated pressure on the board and removed a critical quality hazard. Panel jumpers present similar risks. If insulation covers only the front and back while leaving metal edges exposed, voltage differences between adjacent components can trigger short circuits.
Understanding how photobiomodulation works demands respecting both the biology of cytochrome c oxidase activation and the electrical engineering required to deliver light safely. This dual requirement allows buyers to evaluate devices based on verifiable specifications rather than marketing claims.
Why manufacturing quality defines clinical outcomes
REDDOT LED operates under MDSAP, ISO 13485, CE, RoHS, FCC, ETL, and UKCA standards. Every device undergoes multiple quality inspections and performance tests before export. Compliance is an engineering philosophy applied from the first schematic, not a final checklist.
This discipline drives sustained 50%+ year-over-year sales growth in core international markets, according to REDDOT LED shipment records. B2B partners recognize that reliable photobiomodulation requires a manufacturing partner capable of supporting long-term business growth. Private labeling cannot substitute for optical engineering and firmware development.
When evaluating a light therapy manufacturer, verify these specific capabilities:
- Confirm the factory holds ISO 13485 certification for medical device quality management.
- Request third-party irradiance maps and wavelength verification reports for the exact model.
- Verify compliance with IEC 60601-1 for electrical safety if the device targets clinical use.
- Ask whether the manufacturer handles firmware updates and app integration internally.
- Ensure the supplier provides market-specific documentation for customs clearance.
A device built to these standards delivers consistent LED light therapy benefits because the engineering matches the biology.
Key Takeaways
LED light therapy works by delivering specific wavelengths, typically 660 nm red and 850 nm near-infrared light, to cellular mitochondria to stimulate ATP production without generating thermal damage. Because this mechanism relies on precise photon absorption rather than heat, selecting a device with verified irradiance output and proper optical engineering determines whether a user receives an effective therapeutic dose or simply visible light. Understanding this distinction helps buyers separate clinically relevant photobiomodulation equipment from basic consumer lighting products.
Frequently Asked Questions
What are the negatives of LED light therapy?
The primary risks involve eye strain from improper exposure and inconsistent results from poorly manufactured devices lacking accurate wavelength control. Unlike thermal lasers, PBM does not cause burns, but staring directly at high-irradiance LEDs can irritate the retina, which is why safety goggles are standard practice during sessions. The market’s lack of uniform manufacturing standards means many inexpensive panels fail to deliver the stated irradiance, rendering them ineffective for clinical applications. Organizations like the IEC establish electrical safety standards such as IEC 60601-1 to govern medical-grade light therapy equipment and mitigate these hardware risks.
Do LED light therapy really work?
Yes, photobiomodulation has documented biological effects when delivered at verified wavelengths and sufficient irradiance levels. Peer-reviewed research demonstrates that photons in the 600–700 nm and 800–900 nm ranges are absorbed by cytochrome c oxidase in the mitochondria, increasing cellular energy production. A device advertising 660 nm and 850 nm wavelengths must actually emit those peaks at measurable power to trigger this photochemical response. Manufacturers operating under ISO 13485 quality management systems build devices designed to maintain this optical consistency across production batches.
How many times a day should I do LED light therapy?
Most clinical protocols recommend one session per day, as exceeding the optimal light dose can inhibit the cellular response through a biphasic dose curve. This Arndt-Schulz principle dictates that too little energy produces no effect, while excessive energy suppresses the intended biological activity. Treatment durations generally range from 10 to 20 minutes depending on the device’s irradiance measured in mW/cm² at the treatment distance. Consulting peer-reviewed dosimetry guidelines helps practitioners determine the exact joules per square centimeter required for specific tissue targets.
What not to do after LED light therapy?
Avoid applying photosensitizing topical agents, such as retinoids or strong alpha hydroxy acids, immediately following a session to prevent unexpected skin irritation. Although PBM does not rely on UV radiation or thermal injury, the treated cells undergo active metabolic changes that respond best to standard hydration and gentle care. Users should also avoid exposing the treated area to intense artificial UV sources right after a session. The FDA regulates light-emitting therapeutic products to ensure manufacturers provide clear labeling regarding safe usage parameters and post-treatment precautions.
References & Sources
- International Electrotechnical Commission (IEC). “IEC 60601-1: Medical electrical equipment – General requirements for basic safety and essential performance.”
- International Organization for Standardization (ISO). “ISO 13485: Medical devices — Quality management systems.”
- U.S. Food and Drug Administration (FDA). “Laser Products and Devices / Light-Based Medical Devices.”
- Wikipedia. “Photobiomodulation.”
Related Guides
Understanding Led light therapy how does it work at the cellular level is only the starting point. The practical application depends heavily on matching specific wavelengths, power densities, and treatment durations to distinct biological targets. A device emitting 660 nm red light behaves differently in tissue than one combining red with 850 nm near-infrared, and a seven-wavelength facial mask covering red, blue, green, yellow, purple, cyanine, and white laser options addresses entirely different skin concerns than a single-wavelength sports recovery panel.