
Since 2023, peer-reviewed retinal studies shifted dosing protocols for 660 nm red light for eyes away from the high-intensity exposure limits common in earlier wellness guides.
Applying 660 nm red light for eyes is biologically plausible only when irradiance stays below thresholds that cause thermal stress to retinal tissue. Cytochrome c oxidase absorbs photons near this wavelength. Exceeding safe intensity negates any photochemical benefit.
Understanding how wavelength precision and power density interact determines whether a device supports retinal photobiomodulation or introduces unnecessary risk. The following sections break down the biophysics, manufacturing tolerances, and safety boundaries you need to evaluate any system accurately.
Why 660 nm light matters for the eye: separating biophysics from wellness marketing
Cytochrome c oxidase (CCO) in retinal mitochondria has a primary absorption peak near 660 nm. This single photochemical fact separates genuine photobiomodulation from generic red lighting. When photons at this specific wavelength reach the retina, they are absorbed by CCO within the mitochondrial respiratory chain of retinal ganglion cells. Peer-reviewed findings published in Photobiomodulation, Photomedicine, and Laser Surgery confirm that 660 nm sits directly on this absorption peak, unlike broader visible light wavelengths that scatter without triggering a cellular response.

A common misconception is that any red LED bulb benefits vision. Generic red lighting lacks spectral purity. Even a 10 to 15 nm deviation from the target drastically reduces photon absorption efficiency at the cellular level, rendering the exposure biologically inert. Wavelength selection also depends on tissue depth. While researchers debate whether 630 nm or 660 nm is better for general clinical outcomes, ocular applications specifically study 660 nm due to its transmission properties through the vitreous humor and targeted absorption in the retina.
LED-based photobiomodulation (PBM) differs fundamentally from low-level laser therapy (LLLT). Both can target the retina, but PBM uses non-coherent light with a wider beam profile. This requires strict optical engineering to prevent hot spots, making device design entirely different from laser applications.
How retinal mitochondria respond to 660 nm photons
Photon absorption by CCO triggers a biological cascade: increased adenosine triphosphate (ATP) production, transient release of nitric oxide (NO), and modulation of reactive oxygen species (ROS) in aging retinal cells. Studies published in the British Journal of Ophthalmology demonstrate that precise 660 nm/670 nm interventions improve declining retinal function in older adults by recharging depleted mitochondrial energy reserves.
This cellular response follows a biphasic dose-response curve known as the Arndt-Schulz law. Too little light does nothing. Too much light actively inhibits cellular function and causes oxidative stress. Understanding this threshold determines whether 660 nm red light for eyes acts as a therapy or a hazard.
The irradiance trap: why intensity control dictates safety for 660 nm red light for eyes
Exceeding safe irradiance thresholds turns a therapeutic wavelength into a photochemical hazard for the retina. Consumers and generic device manufacturers frequently assume higher irradiance yields faster results. The retina is uniquely vulnerable to light damage. Pushing milliwatt output past established limits destroys the very cells the treatment intends to support.
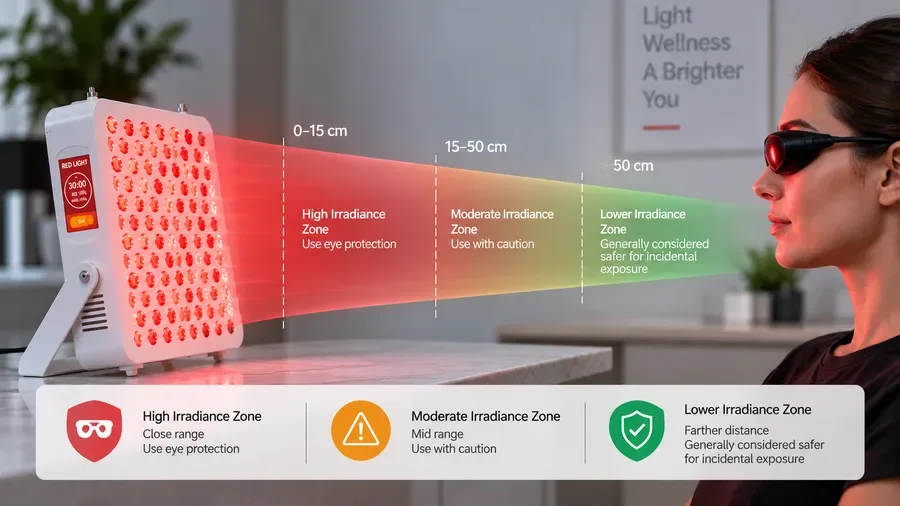
The IEC 62471 standard (Photobiological safety of lamps and lamp systems) and the IES RP-27 series provide the definitive frameworks for categorizing retinal thermal and photochemical risks. These standards dictate strict maximum permissible exposure limits for 660 nm light entering the pupil. Most consumer-grade wellness panels fail to calculate these limits correctly.
Proper dose control requires deliberate optical engineering. REDDOT LED’s T1 Desktop Panel delivers exactly 35 mW/cm² at a 15 cm distance using 120pcs x 1W LEDs paired with a 30-degree lens. This configuration provides sufficient facial or periocular exposure without overwhelming sensitive tissues at close range. By contrast, the Rhinitis Lamp uses 12x3W LEDs to maintain a highly controlled, ultra-low 10 mW/cm² irradiance. Specialized medical devices manage localized exposure by prioritizing precision over raw power output.
Engineering optics to protect the retina
Lens angles dictate light scatter. A 60-degree lens diffuses 660 nm light widely, reducing peak intensity but potentially wasting photons. A 30-degree lens focuses the beam. For devices used near the eyes, selecting the correct lens angle is a critical safety calculation. REDDOT’s 17-member R&D team and portfolio of over 70 patents include proprietary optical designs where lens geometry is explicitly calculated to ensure irradiance remains within IEC 62471 safe limits during OEM/ODM custom builds.
Unregulated devices often advertise high milliwatt outputs without specifying measurement distance or beam angle. These metrics are meaningless without standardized testing conditions. Precise optical control separates a medical instrument from a dangerous novelty.
Misunderstanding NIR targets: confusing 660 nm red light with deep-tissue near-infrared
Wellness blogs frequently conflate 660 nm red light with near-infrared (NIR) wavelengths like 810 nm, 830 nm, or 850 nm. Their biophysical interactions with the eye are entirely distinct. While 660 nm is primarily absorbed by superficial retinal layers and CCO, longer NIR wavelengths penetrate deeper into the choroid and sclera.
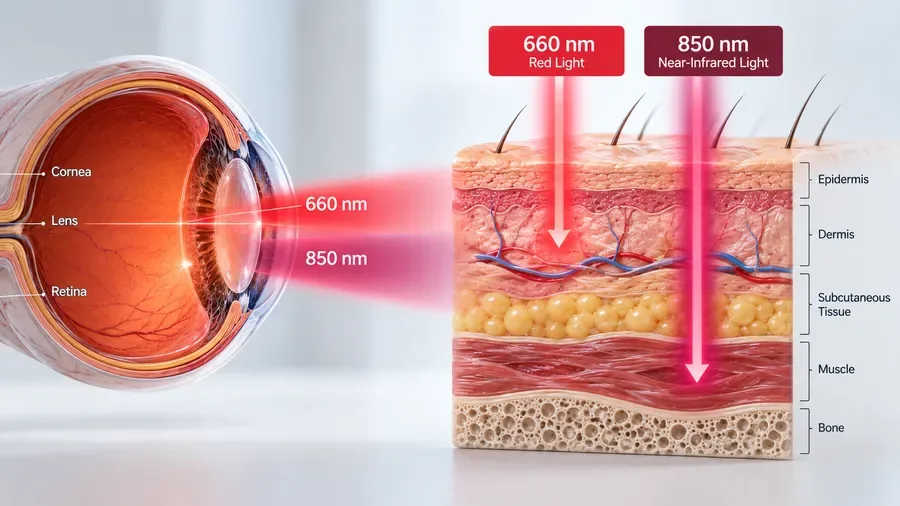
NIR carries a significantly higher risk of invisible thermal accumulation in the lens and retina because it does not trigger the blink reflex or pupillary constriction. While NIR is researched for deeper structural healing, 660 nm remains the focal point for mitochondrial rejuvenation in photoreceptor cells due to its specific absorption spectrum and lower thermal risk profile.
Advanced multi-wavelength devices handle this distinction safely. The PRO300-FS8 Dual-chip Red Light Panel offers 7 adjustable wavelengths (480, 630, 660, 810, 830, 850, and 1060 nm) with independent 0–100% dimming control. Clinical operators can isolate 660 nm for ocular protocols while completely disabling NIR channels, preventing accidental co-exposure. This safety feature is absent in basic consumer panels.
Why mixing wavelengths near the eye requires clinical oversight
Combining 660 nm and NIR simultaneously increases total radiant exposure. Without precise dosimetry, this combination pushes cumulative energy past the safe photochemical threshold defined by IEC 60601-1 for medical electrical equipment. Any device claiming to treat eye conditions using combined red and NIR light must possess documented radiometric testing proving compliance with photobiological safety standards, rather than relying solely on general FCC or CE electronic certifications.
A clinical distributor in North America required high-power, medical-grade panels controllable via smart apps for whole-body use. The manufacturer supplied complete-certification panels with durable protective packaging and plug-and-play hardware. End-user setup time dropped to minutes, achieving a zero-damage delivery rate across all clinics. Separating wavelengths safely at the hardware level prevents cumulative exposure errors before they happen.
Manufacturing realities: what prevents 660 nm wavelength drift in medical devices
A 10 to 15 nm shift in peak emission silently eliminates the therapeutic effect while maintaining the perceived red color. Cheap LEDs degrade over time. As the semiconductor junction heats up or ages, the peak emission drifts away from 660 nm. Affiliate marketers ignore this hidden hardware flaw, but wavelength stability is the foundation of clinical reliability.
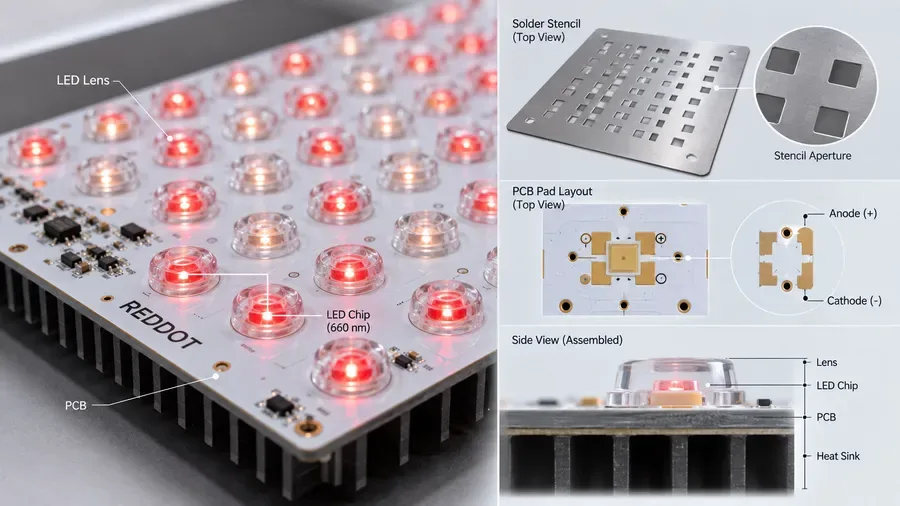
Maintaining exact 660 nm output requires rigorous control over the surface-mount technology (SMT) process. Kevin Zhang, Chief Technology Officer at REDDOT LED, brings over 15 years of experience developing clinically oriented light therapy solutions compliant with IEC 60601-1 safety standards. In his work optimizing SMT processes, two issues consistently caused wavelength instability. First, stencils ordered without considering production requirements led to width mismatches with the squeegee, resulting in poor solder paste application. Second, PCB pad designs for dual-core four-pin LEDs were too small, causing frequent cold joints.
The solution involved establishing a new standard where the stencil’s working area is 6cm wider than the squeegee, and expanding the solder pads for dual-core LEDs by 0.8 to 1 mm on each side. These changes virtually eliminated soldering defects and reduced thermal resistance at the LED junction, locking the 660 nm output within tight tolerances over thousands of hours of use.
REDDOT LED’s ISO 13485-certified quality management system mandates multi-stage inspection processes where every batch undergoes spectrometer testing. This ensures the 660 nm wavelength and irradiance outputs do not drift.
Why medical-grade certification matters for ocular photobiomodulation
ISO 13485 governs the entire lifecycle of a medical device, ensuring traceability, risk management, and consistent performance. Standard consumer electronics marks do not address these factors. REDDOT manufactures under ISO 13485 and MDSAP frameworks across facilities in China and Thailand, providing B2B partners with the regulatory documentation required to legally market 660 nm devices for clinical use in over 50 countries.
Large-scale clinical deployments require sustained, uniform output. The PRO6000-FS7 single chip red light panel, using 1200pcs x 5W LEDs and delivering >124 mW/cm² at 15 cm, is engineered for professional clinic environments where precise, repeatable dosimetry is mandatory. Reliable manufacturing prevents wavelength drift from turning a medical device into an expensive placebo.
Key Takeaways
Cytochrome c oxidase in retinal mitochondria absorbs 660 nm light directly, triggering a photochemical response that broader visible wavelengths cannot replicate. Because the eye is highly sensitive to optical power, any device used near the face must deliver precise irradiance and maintain strict wavelength accuracy rather than relying on raw LED output.
Frequently Asked Questions
Is 660 nm enough for red light therapy?
Yes, 660 nm is sufficient for superficial tissue applications because it aligns with the primary absorption peak of cytochrome c oxidase (CCO) in cellular mitochondria. Research published in Photobiomodulation, Photomedicine, and Laser Surgery confirms this specific wavelength triggers measurable photochemical responses in cells. Deeper tissues often require an 850 nm near-infrared component to achieve adequate penetration, but for skin-level or targeted local use, 660 nm alone drives the biological mechanism.
What wavelength of red light is best for eyes?
The 660 nm wavelength corresponds to the documented absorption peak of CCO within retinal ganglion cell mitochondria. Peer-reviewed findings in Photobiomodulation, Photomedicine, and Laser Surgery identify this specific narrow band as the target for retinal photobiomodulation. Any application directed toward the eyes demands extreme caution regarding irradiance levels, as excessive optical power can cause thermal or photochemical damage regardless of the wavelength selected.
How often should you use 660 nm red light therapy on your face?
Published clinical protocols for facial photobiomodulation typically apply 660 nm light several times per week, though exact session frequency depends entirely on the device’s measured irradiance at the treatment distance. The International Electrotechnical Commission standard IEC 60601-1 governs the electrical and optical safety requirements for medical-grade light therapy equipment used on patients. Consistent, lower-dose sessions generally produce better outcomes than infrequent high-power exposures, which risk exceeding safe energy thresholds for delicate facial skin.
Does red light therapy really help eyesight?
Research into 660 nm photobiomodulation shows measurable effects on retinal mitochondrial function by stimulating cytochrome c oxidase activity. Studies referenced in Photobiomodulation, Photomedicine, and Laser Surgery demonstrate that this specific wavelength interacts with retinal cells at a biochemical level. Translating these cellular mechanisms into verified clinical vision improvement requires controlled dosimetry, and individuals should rely on guidance from qualified eye care professionals rather than consumer-grade devices lacking proper optical engineering.
References & Sources
- International Electrotechnical Commission (IEC). “IEC 60601-1: Medical electrical equipment – General requirements for basic safety and essential performance.”
- Photobiomodulation, Photomedicine, and Laser Surgery. Journal publication covering 660 nm retinal photobiomodulation research.
- U.S. Food and Drug Administration (FDA). “Regulatory oversight of light therapy and photobiomodulation devices.”
- International Organization for Standardization (ISO). “ISO 13485: Medical devices — Quality management systems.”