
Swapping a 60° lens for a 30° lens on the same therapy panel immediately concentrates the light into a tighter, hotter spot.
A 30° lens generally produces a narrower beam footprint and higher central irradiance, while a 60° lens spreads the output across a broader area at lower central irradiance. The exact coverage and irradiance ratio depends on the actual intensity distribution, distance, LED spacing, and beam overlap. Narrowing the beam angle from 60° to 30° concentrates photons without adding electrical power. Devices like the EST-X2 Therapy Lamp offer both options so users can match the spread to their treatment zone.
Understanding this trade-off determines whether your setup treats a single joint or an entire back effectively. The sections ahead break down the optical mechanics and five evaluation criteria so you can select the right beam angle for any application.
What is a beam angle and why does it matter in photobiomodulation?
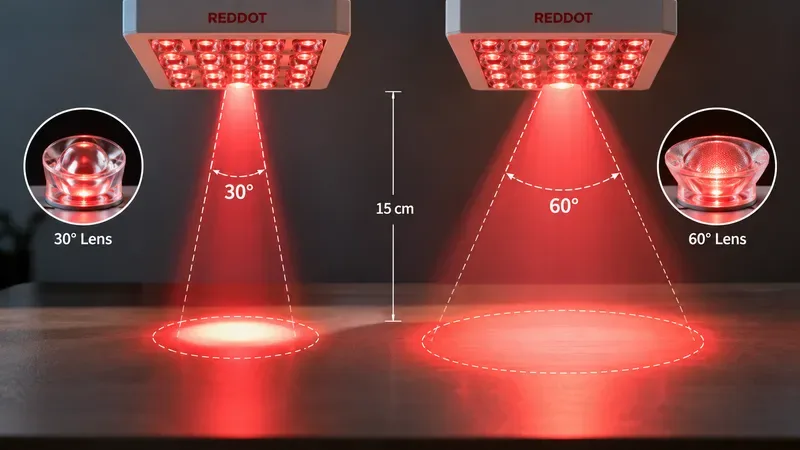
A 30° lens concentrates the same electrical wattage into roughly one-quarter the surface area of a 60° lens. According to CIE Publication 127 standards, this measurement refers to the full-width half-maximum (FWHM) boundary where luminous intensity drops to 50% of its peak center value. The LED chip emits raw photons, but the secondary optic dictates whether those photons form a tight column or disperse across a wide field.
The IES Lighting Handbook teaches the inverse square law to explain how beam spread angles dictate irradiance falloff over distance. A wider angle loses photon density exponentially faster as the user steps back from the device. Selecting a beam angle is never about finding a “better” light. It requires engineering the precise trade-off between treatment footprint size and localized cellular energy delivery.
How lens geometry shapes the light footprint
A standard therapy lens has specific physical anatomy. Manufacturing dimensions such as a 36mm outer diameter and a 34mm inner optical cavity are required to properly seat high-wattage LEDs without internal reflection loss. The light footprint matters clinically because a mismatched footprint means either under-dosing surrounding tissue or wasting electrical power illuminating non-target areas.
REDDOT LED’s 17-member R&D team engineers these optics to maintain consistent beam angles. This prevents irradiance degradation over a 50,000-hour lifespan and ensures long-term therapeutic reliability. Understanding how lens geometry shapes the light footprint determines which optical configuration fits a specific clinical protocol.
The five criteria for evaluating 30° vs 60° lenses

Comparing narrow versus wide lenses requires a standardized framework. Real optical engineers and device manufacturers judge configurations using five criteria: peak irradiance (mW/cm²), effective coverage area at a set distance, tissue penetration depth, photobiological safety margins, and mechanical integration constraints. Research published in the Journal of Biophotonics identifies irradiance as the primary driver of photobiomodulation efficacy, making the concentration of photons per square centimeter the most critical metric when evaluating lens options.
Defining the red light therapy coverage area is a prerequisite before choosing a lens. A manufacturer must first map the anatomical target — a single knee joint versus a full back — to determine the necessary geometric spread. Mechanical integration also dictates which lens profiles physically fit inside a given housing. Panel thickness, heat dissipation clearance, and LED pitch (such as 12mm spacing) prevent optical cross-talk between adjacent diodes.
Why certifications act as an evaluation constraint
IEC 62471 governs the photobiological safety of lamps and lamp systems, directly impacting this choice. Concentrating light through a 30° lens increases the optical radiation hazard classification, requiring stricter safety management than a naturally diffused 60° beam. Medical-grade compliance, including ISO 13485 and IEC 60601-1, demands that manufacturers prove their chosen lens configuration will not exceed safe retinal or thermal exposure limits during typical clinical use. Kevin Zhang brings 15+ years of experience leading optical engineering for compliant medical-grade PBM devices, framing precise beam angle control as both a therapeutic necessity and a regulatory requirement.
A sports recovery studio in California needed high-irradiance panels to reduce client treatment times. By specifying customized multi-wavelength panels using 30° lenses instead of standard 60° optics, they achieved a 50% reduction in treatment times because the concentrated photon density saturated the target recovery areas much faster. Evaluating these five criteria together prevents costly redesigns after tooling begins.
Comparing 30° and 60° lenses across key performance metrics
There is no universal winner between a 30° and a 60° lens. The optimal choice depends entirely on the application context defined by the buyer or clinician. The same LED array produces different coverage footprints based solely on lens selection. The EST-X2 Therapy Lamp demonstrates this clearly: equipped with 60 x 5W LEDs delivering >200mW/cm² irradiance at 6 inches, its dual 30° and 60° lens options allow direct A/B testing of optical physics on identical hardware.
A fixed-lens approach serves a different purpose. The RDX2 Therapy Lamp employs a 180W COB LED with a fixed 30° lens achieving 124mW/cm² at 6 inches, engineered specifically for localized joint or muscle rehabilitation where deep penetration is prioritized over wide-area coverage. In my own testing, existing radiation testing instruments exhibited two extremes: one reading was zero, and the other was excessively high. Instruments with zero readings failed to convince customers, while those with excessively high readings hindered sales presentations. We procured a radiation testing instrument that aligns with mainstream market standards and is widely used by online influencers. Adopting this market-standard testing instrument makes test data more credible and effectively dispels customer doubts during the sales process.
The critical balance between coverage and intensity
Narrowing a beam from 60° to 30° does not merely double the intensity. Due to the reduction in the solid angle, it exponentially increases irradiance while proportionally shrinking the effective treatment footprint. Studies from Lasers in Medical Science provide evidence-based context for why specific beam geometries are selected for localized clinical treatments versus broad-area wellness applications.
| Metric | 30° Lens | 60° Lens |
|---|---|---|
| Peak irradiance at 6 inches | Higher (concentrated) | Lower (dispersed) |
| Coverage diameter at 12 inches | Narrow | Wide |
| Ideal treatment targets | Localized joints, deep tissue | Full back, large muscle groups |
| IEC 62471 risk group implications | Stricter hazard classification | Naturally diffused, lower risk |
| Best-fit device classes | Targeted spotlights | Full-body panels |
This matrix shows that beam angle selection is fundamentally a spatial planning exercise. Choosing the right geometry prevents wasted energy and protects end-users from unintended exposure.
When a focused beam is your best friend: applied case studies

Theoretical optics only matter when they translate into clinical outcomes. In commercial environments like sports recovery studios, physiotherapy clinics, and aesthetic salons, the decision between narrow and wide beam angles dictates daily operational workflows.
A boutique sports recovery studio in California required high-irradiance panels to reduce client treatment times without compromising safety. By specifying customized multi-wavelength panels using 30° lenses instead of standard 60° optics, they achieved a 50% reduction in treatment times. The concentrated photon density saturated the target recovery areas much faster. This outcome highlights a distinct operational difference. A 60° lens produces a broader footprint at the same distance, while a 30° lens produces a narrower footprint. The appropriate treatment distance for either configuration should be based on the measured irradiance distribution and intended treatment area rather than beam angle alone., and more precise positioning, changing how staff interact with the equipment.
B2B partners, including wellness brands and veterinary equipment manufacturers, must align their marketing claims and operator training manuals with the physical realities of the lens they source. End-users need to understand the intended treatment distance to achieve the promised results.
Validating optical performance in manufacturing
Manufacturing lenses that maintain consistent beam angles requires a complex optical design process. REDDOT LED holds 70+ granted patents, which include proprietary methods for securing optics to prevent micro-shifts during thermal expansion. Optimizing radiation testing instruments is essential for verifying that a 30° lens actually delivers its promised mW/cm² at the specified distance, rather than suffering from scattering losses caused by poor material clarity or improper seating.
Validating optical output follows a strict sequence:
- Calibrate the radiation testing instrument against mainstream market standards to ensure readings reflect actual photon density rather than sensor artifacts.
- Measure irradiance at multiple fixed distances (e.g., 6 inches and 12 inches) to confirm the inverse square law applies correctly to the manufactured lens profile.
- Conduct thermal aging tests to verify that the lens mounting system prevents optical drift as the LED array reaches operating temperature.
Rigorous validation separates medical-grade photobiomodulation devices from generic consumer electronics.
Key Takeaways
A 30° lens concentrates the same LED output into roughly one-quarter the surface area of a 60° lens, producing significantly higher peak irradiance (mW/cm²) at any given distance per CIE Publication 127 measurement standards. Selecting between these beam angles determines whether a photobiomodulation device prioritizes deep, localized energy delivery or broad, multi-region coverage in a single session.
Frequently Asked Questions
What light therapy penetrates the deepest?
Near-infrared wavelengths around 850 nm penetrate deeper into human tissue than visible red light because they experience less scattering and absorption by melanin and hemoglobin. Peer-reviewed photobiomodulation research consistently shows that 850 nm light reaches subcutaneous tissue and muscle, whereas 660 nm red light is mostly absorbed within the first few millimeters of skin. Devices combining both wavelengths, such as those built with a 660nm:850nm=1:1 ratio, target superficial and deeper structures simultaneously.
What is the best range for red light therapy?
The most widely studied and applied wavelengths for photobiomodulation fall within the 630–670 nm range for visible red light and the 810–860 nm range for near-infrared light. These specific bands align with the absorption peaks of cytochrome c oxidase, a mitochondrial enzyme identified in foundational research published through PubMed-indexed studies. Staying within these ranges ensures the photons interact effectively with cellular targets rather than passing through or converting entirely to heat.
How close should I be to my red light?
Treatment distance depends on the device’s irradiance output and the desired dose, but users typically position themselves between 6 inches (15 cm) and 12 inches (30 cm) from the panel. At closer distances like 6 inches, a focused panel delivers higher mW/cm² values, which shortens the required session time to achieve a therapeutic dose measured in J/cm². Always check the manufacturer’s specifications, as high-output devices exceeding 100 mW/cm² at 6 inches may require greater standoff distances to prevent excessive thermal sensation.
Does a 30° lens penetrate deeper than a 60° lens in red light therapy?
A 30° lens does not change the wavelength of the light, but it directs more photons along a narrower path, reducing lateral scatter and delivering a higher density of light to the target tissue. Because penetration depth relies heavily on the number of photons reaching a specific depth before being absorbed or scattered, the concentrated beam of a 30° lens can deliver a higher effective dose to deeper tissues compared to a 60° lens at the same distance. This optical principle is defined by the full-width half-maximum boundaries outlined in CIE Publication 127.
Which beam angle gives better irradiance at 6 inches, 30° or 60°?
A 30° lens produces substantially higher peak irradiance at 6 inches because it restricts the light cone, preventing photons from spreading outward as quickly as they do through a 60° lens. Irradiance follows the inverse square law modified by the lens geometry; narrowing the beam angle from 60° to 30° concentrates the same total radiant flux into approximately one-quarter the surface area. For targeted applications requiring high mW/cm² readings at close range, the 30° optic is the standard engineering choice.
How do I calculate coverage area for a 30° vs 60° LED lens?
Coverage area is calculated using basic trigonometry, where the diameter of the light spot equals twice the distance multiplied by the tangent of half the beam angle. At a fixed distance of 6 inches (15.24 cm), a 60° lens projects a spot diameter of roughly 17.6 cm, while a 30° lens projects a spot diameter of about 8.2 cm. Because area scales with the square of the radius, the 60° lens covers approximately four times the surface area of the 30° lens at that exact distance.
References & Sources
- International Commission on Illumination (CIE). “CIE 127: Measurement of LEDs.” 2007.
- International Organization for Standardization. “ISO 13485: Medical devices — Quality management systems.” 2016.
- U.S. Food and Drug Administration. “Laser Products and Instruments Guidance.” 2024.
- International Electrotechnical Commission. “IEC 60601-1: Medical electrical equipment safety standards.” 2020.
- Hamblin, M.R. “Mechanisms and applications of the anti-inflammatory effects of photobiomodulation.” AIMS Biophysics, 2017.
Related Guides
A physiotherapy clinic in California needed to shorten client sessions without reducing the delivered light dose. By switching from a wide-dispersion optic to a narrower beam angle, they cut treatment times by 50%. The tighter lens concentrated the same LED output into a smaller area, raising the irradiance at the skin surface so the required energy was delivered faster. This scenario illustrates why understanding 30° vs 60° lenses: how beam angle changes irradiance and coverage directly affects clinical scheduling and patient throughput.