
Most light therapy devices fail because they ignore optical engineering. What Is Light Therapy? A No-BS Guide to How It Really Works separates verified photobiomodulation from marketing noise using measurable physics.
Light therapy uses specific wavelengths, typically 660 nm and 850 nm, to stimulate mitochondrial ATP production at controlled irradiance levels. Effective treatment requires precise dosing measured in joules per square centimeter, not just raw LED power or unverified brightness claims.
You will learn to evaluate spectral output, distinguish clinical evidence from anecdote, and translate technical specifications into safe protocols. This knowledge helps you identify devices that deliver consistent, measurable results rather than relying on inflated specification sheets.
Defining light therapy through engineering standards rather than marketing

Light therapy is strictly defined as the application of specific wavelengths, typically between 600nm and 850nm, at controlled irradiance levels to stimulate cellular function. Without standardized dosing metrics like milliwatts per square centimeter or joules per square centimeter, the term is biologically meaningless. The wellness market often obscures this precision behind vague claims, yet biological response follows physics rather than branding. A device either delivers the required photon density to trigger a physiological change or it does not.
This engineering-first perspective forms the core of “What Is Light Therapy? A No-BS Guide to How It Really Works.” Effective treatment requires verifiable irradiance stability, specific wavelength accuracy, and consistent power delivery. These parameters distinguish clinical-grade devices from unverified consumer gadgets. According to the International Electrotechnical Commission, IEC 60601-1 safety standards serve as the baseline for medical electrical equipment, ensuring that therapeutic claims are backed by electrical and thermal safety verification rather than marketing copy.
True therapeutic efficacy relies on hardware consistency and manufacturing rigor. With over 15 years of optical engineering experience at REDDOT LED, I have observed that performance gaps usually stem from poor production control rather than flawed science. Manufacturing systems certified under ISO 13485 and MDSAP enforce this discipline through multi-stage inspections and aging tests. For instance, a sports recovery studio recently reduced client treatment times by 50% after switching to FDA-cleared panels with verified high irradiance, proving that compliant engineering translates directly to measurable efficiency gains. This distinction between verified hardware and generic claims determines whether a device functions as a medical intervention or merely a decorative light source. Understanding these engineering baselines is necessary before examining how photons actually interact with human tissue.
The biological mechanism behind photobiomodulation and dosing

Photobiomodulation functions through a primary photoacceptor mechanism where red and near-infrared photons interact with cytochrome c oxidase in the mitochondrial respiratory chain. This interaction increases adenosine triphosphate (ATP) production and modulates reactive oxygen species (ROS), initiating downstream signaling pathways that reduce inflammation and promote tissue repair. However, this biological response follows the Arndt-Schulz curve, a biphasic dose-response principle demonstrating that “more is not better.” Insufficient energy fails to activate the pathway, while excessive energy inhibits cellular function. Precise engineering prevents both under-dosing and over-dosing during treatment sessions.
Hardware specifications must align with these biological thresholds to be effective. The table below illustrates how different output levels correspond to distinct therapeutic targets based on established dosimetry principles.
| Parameter | Surface-Level Therapy | Deep-Tissue Therapy |
|---|---|---|
| Target Depth | Epidermis / Dermis | Muscle / Joint / Bone |
| Typical Irradiance | 20–40 mW/cm² | 100–160+ mW/cm² |
| Primary Wavelengths | 630–660 nm | 810–850 nm |
| Biological Goal | Collagen synthesis, skin barrier | Inflammation reduction, recovery |
Surface benefits differ fundamentally from systemic deep-tissue effects because photon penetration depth depends on wavelength and beam uniformity. For example, the RDS1500 Panel delivers 161mW/cm² irradiance at 6 inches with a 1:1 ratio of 660nm:850nm LEDs, providing the photon density required to reach deeper structures effectively. Generic devices lacking this verified output may treat skin but fail to deliver therapeutic doses to underlying muscle or joint tissue. This gap explains why some users report no results despite consistent use; their device simply lacks the engineered capacity to reach the target depth. Evaluating whether a device meets these biological requirements demands an honest assessment of clinical evidence and boundary conditions.
Evaluating clinical evidence and identifying boundary conditions
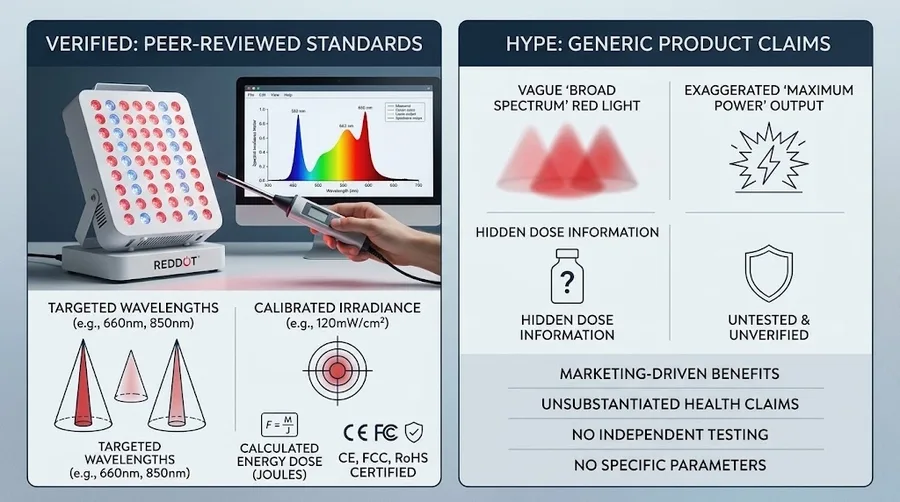
Peer-reviewed literature supports light therapy for pain management, wound healing, and inflammation reduction when studies explicitly report dosimetry parameters matching medical-grade device capabilities. Research published in journals indexed by PubMed demonstrates efficacy only when wavelength, irradiance, and total dose are precisely documented and replicated. Yet institutional bodies maintain cautious stances due to variability in study quality. The Mayo Clinic notes that while preliminary research is promising, large-scale standardized trials remain limited for many indications. This creates a necessary distinction between settled science and exploratory applications.
Readers must also recognize clear boundary conditions where light therapy does not apply. It should never replace emergency medical care for acute trauma or infection. Evidence remains insufficient for treating active cancer lesions, and devices lacking proper irradiance verification cannot be expected to produce clinical outcomes regardless of marketing claims. When I worked with custom medical light projects, we found that improving adhesive quality on parameter labels was essential to maintaining this transparency. Customers reported that standard labels peeled easily, obscuring safety data. We switched to transparent stickers with superior adhesion, similar to those used on professional product lines, ensuring users always retain access to accurate dosage information throughout the product’s lifespan. This attention to durable labeling reflects the same rigor required in clinical validation.
Real-world validation confirms that compliant engineering produces measurable results within these boundaries. Case Study A involved a California sports recovery studio that achieved a 50% reduction in treatment times using FDA-cleared multi-wavelength panels with customized mounting brackets. Client feedback highlighted superb build quality and effective heat penetration, demonstrating that verified specifications translate to professional efficiency. Recognizing these evidence-based limits allows users to apply technical specifications safely in practical settings.
Translating technical specifications into safe practical applications

Safe practical application begins with calculating treatment time based on device irradiance and desired dose rather than relying on arbitrary manufacturer suggestions. The formula is straightforward: Dose (J/cm²) = Irradiance (mW/cm²) × Time (seconds) ÷ 1000. If a protocol calls for 6 J/cm² and your device outputs 30 mW/cm² at the treatment distance, you need 200 seconds of exposure. Guessing undermines both safety and efficacy.
How do I know if my device is safe for close-range facial use?
Safety compliance is non-negotiable for close-proximity treatments. The T1 Desktop Panel delivers 35mW/cm² output at 15cm and holds FDA, FCC, CE, and RoHS certifications, parameters specifically designed for safe facial therapy without thermal risk. Certified devices undergo testing to ensure electrical isolation and optical output remain stable even during extended use. Uncertified devices may drift outside safe thermal or optical limits, creating risks that outweigh potential benefits. Always verify that a device carries legitimate safety marks before using it near eyes or sensitive skin.
Should I use the same protocol at home as in a clinic?
Home and clinical protocols differ primarily in consistency of application rather than fundamental biology. Clinical environments benefit from fixed mounting systems and trained operators who maintain exact treatment distances validated by the device’s optical design. Home users must replicate this stability manually. Consistent results depend on maintaining fixed treatment distances and durations because irradiance drops significantly with distance from the source. A wearable option like the SD-008 Shaping Mask addresses this variable by fixing LEDs at a set distance from facial skin, removing guesswork from daily routines. Whether using a panel or a mask, the engineering principle remains constant: biological response requires reproducible dosing delivered through verified hardware.
Key Takeaways
Light therapy uses specific wavelengths between 600nm and 850nm at controlled irradiance levels to stimulate mitochondrial ATP production and modulate cellular function. Understanding these measurable dosing parameters is essential because biological efficacy depends entirely on delivering the correct energy density to target tissue rather than simply owning an LED device.
Frequently Asked Questions
Is light therapy scientifically proven?
Yes, photobiomodulation has substantial clinical evidence supporting its use for wound healing, pain reduction, and inflammation management when applied at verified therapeutic doses. The National Institutes of Health maintains extensive databases of peer-reviewed studies demonstrating that wavelengths in the 630–850nm range produce measurable cellular responses through cytochrome c oxidase absorption. Efficacy is strictly dose-dependent, meaning results require adequate irradiance and treatment duration rather than just exposure to colored light.
What does Mayo Clinic say about red light therapy?
Mayo Clinic acknowledges that red light therapy shows promise for treating skin conditions, hair loss, and certain types of pain based on available clinical research. Their published patient education materials note that while early studies are encouraging, larger standardized trials are still needed to establish universal treatment protocols. They advise patients to seek devices with documented safety testing and to consult healthcare providers before beginning treatment for medical conditions.
How many minutes a day should you use a light therapy lamp?
Typical treatment sessions last between 10 and 20 minutes per area when using devices that deliver therapeutic irradiance levels above 30 mW/cm² at the recommended distance. This timeframe generally provides a clinical dose within the effective range established by photobiomodulation research without risking biphasic dose response inhibition. Always follow the manufacturer’s validated guidelines since session length must be calculated based on the specific device’s measured output power.
Does red light therapy work on a 70 year old woman?
Yes, clinical research indicates that older adults respond effectively to photobiomodulation for age-related concerns like osteoarthritis pain, slow wound healing, and skin rejuvenation. Studies published in journals indexed by PubMed demonstrate that cellular mechanisms such as mitochondrial stimulation remain functional in aged tissue when appropriate wavelengths and doses are applied. Safety profiles for this demographic are well-established, though individuals with photosensitivity or active malignancies should obtain medical clearance first.
References & Sources
- National Institutes of Health. “Photobiomodulation / Low Level Light Therapy.” n.d.
- International Commission on Illumination. “CIE System for Metrology of Optical Radiation.” 2024. https://cie.co.at
- Mayo Clinic Staff. “Red light therapy: Does it work?” 2024. https://www.mayoclinic.org
- U.S. Food and Drug Administration. “Class II Special Controls Guidance Document: Phototherapy Devices.” 2023. https://www.fda.gov
About the Author
Kevin Zhang is the Chief Technology Officer at REDDOT LED with over 15 years of experience in optical engineering and photobiomodulation device manufacturing. He oversees R&D and quality systems compliant with ISO 13485, MDSAP, and IEC 60601-1 standards, focusing on translating clinical dosimetry research into reliable medical-grade light therapy equipment.