
By 2024, updated dosimetry research made the old debate over whether 810 or 830 red light therapy is better largely irrelevant.
Both 810nm and 830nm have been used in PBM research. Their suitability depends on the specific protocol, optical output, dose, tissue target, treatment geometry, and supporting evidence rather than a universal rule assigning 810nm to one anatomical target and 830nm to another.; clinical outcomes depend on irradiance accuracy and optical design more than a 20nm wavelength gap. Both wavelengths target cytochrome c oxidase in mitochondria to support cellular energy production. Manufacturing tolerances often shift actual LED output by several nanometers anyway.
Understanding how lens optics and thermal management affect your chosen wavelength helps you evaluate devices accurately. You will learn what specifications actually drive tissue penetration so you can compare panels or targeted tools with confidence.
The photobiology behind 810nm and 830nm near-infrared light

When evaluating whether is 810 or 830 red light therapy better, the answer begins inside the mitochondria. Peer-reviewed data published in the journal Photobiomodulation, Photomedicine, and Laser Surgery details how cytochrome c oxidase (CCO), a primary enzyme in the cellular respiratory chain, absorbs specific near-infrared light bands to drive adenosine triphosphate (ATP) production. Both 810nm and 830nm fall within this active absorption window, but they interact with CCO through slightly different action spectra.
A common misconception is that CCO acts as the sole receptor for all near-infrared effects. In reality, water molecules and other secondary chromophores absorb light at these wavelengths too, generating localized tissue heating and triggering non-thermal signaling pathways. This means the biological response depends on more than just mitochondrial stimulation.
The World Association for Photobiomodulation Therapy (WALT) has established consensus statements defining recommended dosage guidelines and fluence parameters for clinical use. WALT protocols place both 810nm and 830nm within accepted ranges, though specific applications differ. Neurological protocols often favor 810nm, while musculoskeletal applications frequently specify 830nm.
While both wavelengths are effective, their 20-nanometer spectral difference dictates distinct biological interaction profiles. Buyers must look beyond generic wavelength charts to understand how these optical properties translate into actual device performance.
Why cytochrome c oxidase drives the wavelength debate
CCO exhibits specific absorption peaks across the near-infrared spectrum. Research comparing cellular ATP production responses shows that 810nm aligns closely with one of these peak absorption bands, giving it a theoretical advantage for rapid mitochondrial activation. However, 830nm also stimulates CCO effectively, often producing sustained responses in denser tissues where deeper photon penetration matters more than peak enzymatic affinity. These baseline scientific findings establish the context before engineering variables enter the equation.
Secondary chromophores and the limits of single-receptor models
Light scattering and absorption by tissue water create different thermal pathways at 810nm versus 830nm. Water absorption increases slightly at longer near-infrared wavelengths, meaning 830nm generates marginally more localized heat in hydrated tissues. Relying solely on CCO affinity oversimplifies device selection for deep tissue recovery or brain stimulation protocols. Understanding these secondary interactions explains why optical engineering ultimately determines therapeutic success.
What optical physics reveals about tissue penetration differences

Quantitative findings published in the Journal of Biophotonics map the differences in scattering coefficients and penetration depths between 810nm and 830nm light through human tissue types, including skin, subcutaneous fat, and skeletal muscle. Longer near-infrared wavelengths generally experience less scattering in dense biological media. This physical property allows 830nm photons to maintain directional coherence deeper into muscle tissue compared to 810nm.
These optical physics numbers carry direct implications for end users. A lower scattering coefficient does not automatically equal better therapeutic outcomes if the target depth is shallow. For superficial skin applications, the difference is negligible. But for deep joint recovery, scattering behavior becomes the deciding factor.
Clinical scenarios highlight this contrast clearly. Transcranial applications targeting neurological support often favor 810nm due to its specific skull penetration metrics and alignment with neural chromophore absorption. Deep muscular repair, conversely, benefits from the reduced scatter of 830nm. Comparing near-infrared wavelengths requires looking at these penetration metrics alongside device power output rather than evaluating wavelength in isolation. A portable 9W flashlight emitting 850nm light, for example, behaves entirely differently at the tissue level than a high-powered clinical panel running the same diode.
Scattering coefficients in skin versus deep muscle
Journal of Biophotonics data demonstrates that 830nm light travels further through dense muscle fascia before losing therapeutic intensity compared to 810nm. Under identical irradiance conditions, an 830nm beam reaches a deep tendon more effectively because fewer photons deflect laterally in the subcutaneous fat layer. Skin, being thinner and less dense, presents minimal resistance to either wavelength. Muscle density is where the divergence becomes measurable.
Matching the wavelength to the anatomical target
B2B product developers must map specific body parts to the optimal near-infrared wavelength based on penetration data. Superficial skin wounds respond well to 810nm. Deep knee joints or hip capsules require the penetration profile of 830nm. Aligning the chosen wavelength with the intended anatomical use case ensures clinical efficacy and prevents wasted development cycles. This anatomical mapping directly informs the manufacturing tolerances required for consistent delivery.
Why manufacturing tolerances matter more than the 20nm gap
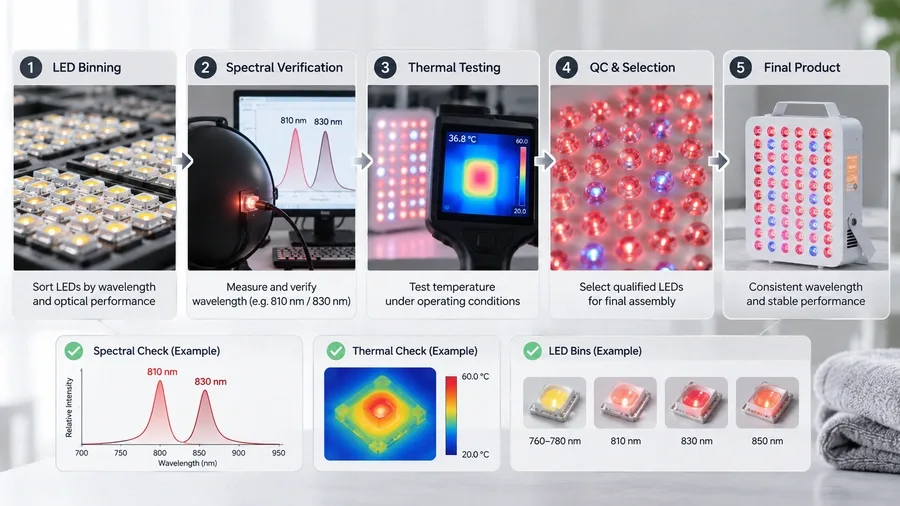
Theoretical biology means little without optical engineering realities. Kevin Zhang, Chief Technology Officer at REDDOT LED, brings over 15 years of experience developing patented light therapy products compliant with IEC 60601 safety standards. That background reveals a persistent industry problem: a manufacturer claiming “810nm” or “830nm” is usually stating a nominal peak. Without strict wavelength binning consistency, the actual spectral output drifts significantly during operation, erasing any theoretical advantage of one wavelength over the other.
REDDOT LED operates under an ISO 13485-certified quality management system. Multi-stage performance testing ensures that the company’s 70+ patented technologies maintain strict spectral accuracy across mass production batches. This prevents the counterfeit wavelength problem common among suppliers who prioritize cost reduction over optical precision.
The International Electrotechnical Commission standard IEC 60601-2-57 specifies essential performance requirements for non-laser light source equipment. It governs spectral accuracy and irradiance tolerances that reputable manufacturers must meet. When asking is 810 or 830 red light therapy better, the specification sheet only tells half the story; the manufacturing tolerance tells the rest.
The reality of LED binning and spectral drift
Wavelength binning is the process of sorting LEDs after manufacturing based on their exact peak emission. Cheaper suppliers mix bins to reduce waste, resulting in devices that emit a broad, ineffective spectrum rather than a precise 810nm or 830nm peak. Thermal management compounds this issue. If a device lacks proper heat sinking, an 810nm LED might drift toward 820nm under load, making the initial specification meaningless.
When assembling the RDPRO-6000 single-core seven-channel product, the original 70cm terminal wire length proved insufficient due to the excessive distance between the lamp board solder joints and the constant current board. Cutting terminals and splicing extension wires increased labor time and risked voltage drop, which causes uneven brightness. Adjusting the layout of the constant current board on the housing shortened its distance from the lamp board, solving the wire length problem without altering the wiring itself. Adding eight rivets to the housing accommodated different mounting hole positions for red and infrared constant current boards. Precision in physical engineering directly impacts thermal dissipation, which dictates whether the LED maintains its exact wavelength during a full treatment session.
How ISO 13485 certification guarantees wavelength fidelity
Does an ISO 13485 certification actually affect the wavelength my device emits? Yes. ISO 13485 defines design control, verification, and validation requirements for medical devices. It ensures claimed peak wavelengths remain consistent throughout manufacturing batches regardless of the buyer’s country. This regulatory framework forces documented verification at every production stage.
Why do some panels lose their specified wavelength after a few months of use? Spectral drift occurs when thermal management fails or when manufacturers use mixed-bin LEDs without proper testing. Professional OEM/ODM partners prevent this through multi-stage inspection and aging tests, separating reliable engineering from basic private-label assembly. Consistent quality relies on standardized production processes rather than luck.
How irradiance and lens optics interact with 810nm or 830nm selection
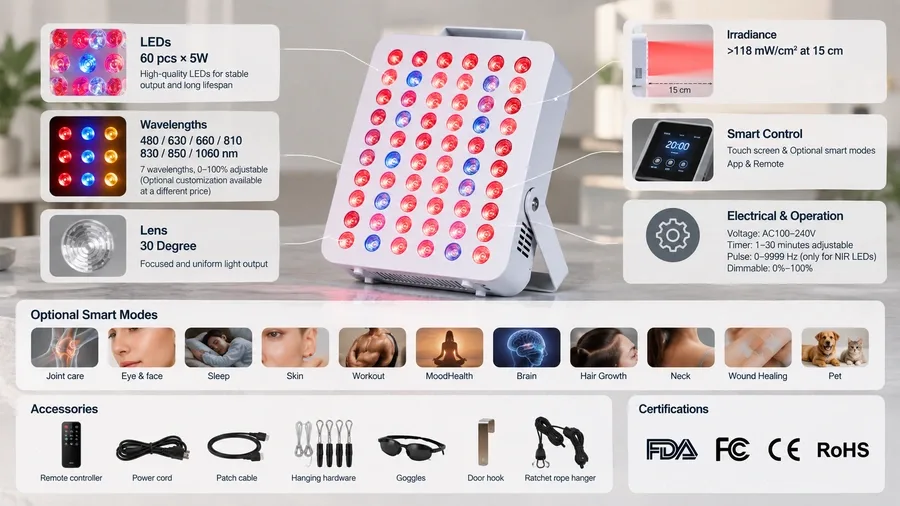
Biological data and manufacturing tolerances only matter if the device architecture delivers photons to the target tissue at a therapeutic dose. Irradiance levels and lens configurations determine whether a chosen 810nm or 830nm wavelength actually penetrates to the required depth.
The EST-X2 Therapy Lamp illustrates high-output engineering. It uses 60 X5W LEDs with a 660nm:850nm=1:1 wavelength ratio, delivering >200mW/cm² irradiance at a 6-inch platinum LED distance. Optional 30-degree and 60-degree lens configurations alter the photon density delivered to deep tissues. A narrow 30-degree lens concentrates energy for joint recovery, while a 60-degree lens covers broader areas.
Close-range applications require a different engineering approach. The T1 Desktop Panel uses 120 × 1W LEDs with a 660nm:850nm ratio of 1:1, delivering an irradiance of 35 mW/cm² at 15 cm for desktop use. Application depth influences wavelength selection, optical configuration, and device design. REDDOT LED provides OEM and ODM services for wavelength ratio and optical configuration customization, enabling brands to develop devices with either 810nm- or 830nm-focused designs based on their target applications and market positioning.
Engineering high irradiance for deep tissue targets
The mathematical relationship between LED wattage, lens angle, and working distance dictates therapeutic success. A narrow 30-degree lens is often mandatory when using 830nm for deep joint recovery to prevent photon scatter before the light reaches the target capsule. Large-format devices manage power distribution differently. The YD007 Red Light Therapy Mat uses 945pcs LED beads with a 4:1 ratio of 660nm to 850nm wavelengths and 5 adjustable gears (P1-P5) to maintain consistent irradiance across a 160x60cm surface area. Distributing power evenly prevents hot spots while ensuring adequate total dosage.
Optimizing optics for targeted, close-range applications
Why shouldn’t I just buy the highest irradiance panel available for every application? Wider beam angles and lower overall power are preferable for superficial or localized treatments. Excessive irradiance at shallow depths triggers biphasic dose response inhibition, where overdosing the tissue cancels out the therapeutic benefit. Flexible form factors balance portability with sufficient spectral delivery. The YD004 Red Light Therapy Belt uses 210pcs LEDs with a 660:850 4:1 ratio and 36W power at 12V/3A input, providing targeted waist or leg therapy without overwhelming superficial cells. Even compact wearable solutions, like an 18W therapy belt using 105pcs LEDs at a 660:880 3:2 ratio, demonstrate that precise dosing outweighs raw power for daily localized care. Optics must match the anatomy.
Clinical use cases where the right near-infrared wavelength drives outcomes

Laboratory specifications mean nothing without real-world application. Consider a California sports recovery studio that needed to reduce client treatment times without compromising safety. Supplying FDA-cleared, multi-wavelength panels with customized mounting brackets solved the problem. Treatment times dropped by 50%, driven by high-irradiance deep heat penetration. Client feedback highlighted superb build quality.
This outcome was not accidental. The 50% time reduction resulted directly from aligning wavelength selection with deep-penetrating near-infrared optics, strict manufacturing binning, and optimized lens configurations. High irradiance paired with accurate emission allowed the clinic to deliver therapeutic doses faster.
B2B buyers and product developers face distinct engineering choices based on their target market. A physiotherapy clinic device focused on deep tissue repair favors precise 830nm optics and high mW/cm² output. A consumer wellness brand targeting cognitive support leans toward 810nm transcranial protocols. REDDOT LED serves as a long-term development partner for medical device manufacturers, wellness brands, and sports recovery companies across more than 50 countries, helping them translate these wavelength specifications into reliable, market-ready products.
Sports recovery and deep joint rehabilitation
Clinics and gyms evaluate device specifications based on the necessity of high mW/cm² output paired with accurate 830nm emission to treat dense muscle tissue and joint capsules effectively. Customized mounting brackets ensure the panel stays at the optimal distance from the patient. Adjustable pulse frequencies, such as the 10Hz and 40Hz options available on REDDOT systems, allow practitioners to tailor the photobiomodulation dose for athletic recovery. Specific hardware configurations turn general wavelength theory into repeatable clinical results.
Neurological support and targeted cellular therapies
How do developers verify that a device actually emits the 810nm wavelength claimed for brain health applications? Emerging protocols for transcranial photobiomodulation frequently research 810nm for its specific interaction with neural tissue and skull penetration characteristics. Product developers must verify spectral purity through multi-stage performance testing when designing devices for sensitive neurological applications. Relying on nominal specifications without independent validation risks delivering ineffective or unsafe doses to vulnerable populations. Testing confirms what spec sheets merely promise.
Key Takeaways
Both 810nm and 830nm wavelengths effectively stimulate cytochrome c oxidase in the mitochondria, with 810nm aligning more closely to the primary near-infrared absorption peak documented in photobiomodulation research. Selecting between them depends less on a universal superiority and more on matching the device’s irradiance output, optical lens design, and thermal management to your specific treatment depth requirements. Understanding these engineering variables matters because a well-manufactured panel at either wavelength will consistently outperform a poorly cooled unit that drifts from its stated specification during use.
Frequently Asked Questions
Is 810nm or 830nm better for deep tissue penetration?
Both 810nm and 830nm penetrate deeper into tissue than visible red light wavelengths like 660nm. According to optical physics principles outlined by the International Commission on Illumination (CIE), near-infrared light in the 800–850nm window experiences lower scattering and reduced absorption by melanin and water compared to shorter wavelengths. The 20nm difference between 810nm and 830nm produces negligible variation in absolute penetration depth; reaching muscle or joint tissue depends far more on the device delivering sufficient irradiance, typically above 30 mW/cm² at the treatment distance, to push photons past the skin barrier.
What is the difference between 810nm and 830nm red light therapy?
The primary difference lies in their exact position on the near-infrared absorption spectrum relative to cellular chromophores. Research published in Photobiomodulation, Photomedicine, and Laser Surgery identifies 810nm as sitting directly on a major absorption peak of cytochrome c oxidase. While 830nm falls slightly off this specific peak, it remains within the broader therapeutic window where mitochondrial stimulation occurs, meaning both wavelengths trigger similar photobiomodulation pathways despite the 20nm spectral gap.
Does the 20nm difference between 810 and 830 actually matter clinically?
In most practical applications, a 20nm spectral shift does not produce drastically different clinical outcomes. Peer-reviewed studies indexed on PubMed generally treat the 800–850nm band as a single therapeutic window for near-infrared photobiomodulation. Clinical results depend much more heavily on total energy delivered, measured in Joules per square centimeter (J/cm²), and whether the manufacturer maintains tight LED binning tolerances so the actual emitted light stays at the target wavelength rather than drifting under heat.
Which near-infrared wavelength is best for brain health and neurological support?
Research exploring transcranial photobiomodulation frequently uses 810nm due to its alignment with the cytochrome c oxidase absorption peak and its ability to pass through the skull. Studies available through the National Institutes of Health (NIH) have investigated 810nm light for cognitive support and neurological recovery. Achieving measurable effects requires devices engineered to deliver adequate power density through bone, making precise optical design and verified irradiance outputs non-negotiable for any equipment intended for cranial application.
How do manufacturing tolerances affect 810nm and 830nm LED performance?
Manufacturing tolerances dictate whether an LED actually emits at 810nm or 830nm, or if it drifts significantly when the device heats up. Under international standards such as IEC 60601-1, medical-grade electrical equipment must demonstrate consistent performance and safety limits. Low-cost LEDs without strict binning can shift several nanometers during operation, moving the output away from the optimal absorption peak. Quality systems like ISO 13485 require multi-stage inspection and aging tests to verify that every production batch maintains its specified wavelength and irradiance consistency.
Can I get a device that combines both 810nm and 830nm wavelengths?
Some manufacturers produce multi-wavelength panels that combine various near-infrared diodes, though combining 810nm and 830nm specifically is less common than pairing a visible red wavelength like 660nm with a single near-infrared wavelength like 850nm. Custom OEM/ODM engineering allows brands to specify exact diode combinations based on their target market requirements. When evaluating a multi-wavelength device, verify that the manufacturer provides independent spectral test reports confirming the output ratio and total irradiance for each individual wavelength present.
What does the WALT recommend regarding 810nm vs 830nm dosages?
The World Association for Photobiomodulation Therapy (WALT) publishes dosage guidelines based primarily on broad wavelength bands rather than splitting recommendations between 810nm and 830nm. WALT protocols typically define target doses in J/cm² for near-infrared wavelengths falling within the 780–860nm range. Following these established dosimetry guidelines helps ensure treatments deliver enough energy to stimulate cellular activity without exceeding thresholds where photobiomodulation effects diminish.
How does irradiance impact the effectiveness of 810nm or 830nm light?
Irradiance, measured in milliwatts per square centimeter (mW/cm²), determines how quickly a therapeutic dose of light energy reaches the target tissue. A device emitting at 810nm with low irradiance will take significantly longer to deliver the required J/cm² compared to a high-output panel operating at the same wavelength. For example, professional-grade panels often deliver over 100 mW/cm² at close range, allowing treatment sessions to remain short while still achieving the total energy dosage recommended by photobiomodulation research.
References & Sources
- International Commission on Illumination (CIE). “Optical Radiation and Photobiology.”
- National Institutes of Health (NIH). “Photobiomodulation and Near-Infrared Light Research.”
- International Electrotechnical Commission (IEC). “IEC 60601-1 Medical Electrical Equipment Standards.”
- International Organization for Standardization (ISO). “ISO 13485 Medical Device Quality Management Systems.”
- Hamblin, M.R. “Mechanisms and Mitochondrial Redox Signaling in Photobiomodulation.” Photochemistry and Photobiology. 2018.
- World Association for Photobiomodulation Therapy (WALT). “Dosage Recommendations for Low-Level Light Therapy.”