
Light therapy works when specific wavelengths of light penetrate tissue and trigger measurable chemical changes inside your cells. Most explanations bury that simple fact under jargon.
How Does Light Therapy Actually Work? A No-BS Guide to the Science: it functions because photons at 660 nm and 850 nm are absorbed by mitochondria, accelerating ATP production. This cellular energy boost drives tissue repair. Devices like the RD7 7 Color LED Facial Mask apply these exact wavelengths directly to skin.
You will learn how to evaluate irradiance numbers, spot weak optical designs, and calculate a dose that produces real results. Understanding these variables separates devices that change tissue from those that just glow.
Turning light into cellular fuel: the photobiology behind the process
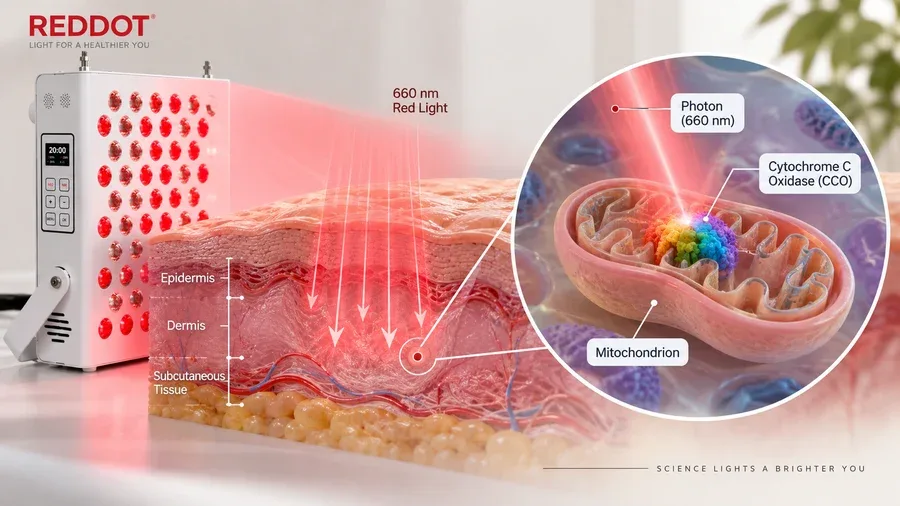
Light therapy works through a photochemical reaction inside your cells. When specific wavelengths of light hit tissue, they are absorbed by cytochrome c oxidase, the terminal enzyme in the mitochondrial respiratory chain. Foundational research published in Photobiomodulation, Photomedicine, and Laser Surgery establishes that this absorption triggers an increase in adenosine triphosphate (ATP) production. The cell literally turns light energy into chemical fuel.
This is a precise biochemical event. The biological response depends entirely on delivering the correct photon density to the target tissue, a variable often glossed over in consumer marketing. Too little light produces no effect. The optimal dose stimulates cellular repair. Excessive doses can inhibit function. This relationship follows the biphasic dose response curve, also known as the Arndt-Schulz curve. Consensus papers from the World Association for Photobiomodulation Therapy (WALT) define the therapeutic windows where this stimulation occurs safely.
Historically, PBM sat on the fringe of medicine because early laser sources delivered unpredictable doses. As optical engineering advanced, manufacturers learned to produce consistent, measurable light output, moving the practice into accepted clinical use. Understanding how does light therapy actually work requires accepting that biology demands exact physics.
Why wavelength precision dictates biological response
Red light between 630nm and 670nm absorbs primarily in the epidermis and dermis. Near-infrared light between 810nm and 850nm penetrates deeper into muscle and joint tissue, according to established Optica research on tissue optics. A device emitting “around 660nm” is scientifically insufficient. Wavelength accuracy matters because different wavelengths have different absorption, scattering, and tissue-penetration characteristics. However, PBM devices typically emit across a finite spectral bandwidth rather than at a single exact wavelength.
The T1 Desktop Panel illustrates this requirement. It uses 120 individual 1W LEDs locked to a strict 660nm:850nm 1:1 wavelength ratio, achieving 35mW/cm² irradiance at 15cm. Balanced dual-wavelength delivery must be precisely calibrated for close-range cellular absorption rather than left to generic LED bins. Wavelength accuracy separates functional medical devices from colored lamps.
Preparing the variables: what must be true before light therapy works
Understanding the cellular mechanism means nothing if the hardware cannot deliver the required parameters. Effective PBM demands accurate wavelength emission, sufficient irradiance measured in mW/cm², appropriate treatment distance, and thermal stability. Kevin Zhang, Chief Technology Officer at REDDOT LED, brings over 15 years of experience to this reality: light therapy efficacy is fundamentally an engineering challenge. The goal is delivering precise photons to tissue without causing thermal degradation to either the LEDs or the patient’s skin.
Optical design dictates whether those photons arrive intact. The EST-X2 Therapy Lamp uses 60 5W LEDs delivering >200mW/cm² irradiance at 6 inches. It pairs these with specific 30-degree and 60-degree lens options to control photon density for targeted versus broad-area photobiomodulation. Without these lenses, light scatters uselessly before reaching the target depth. Safety standards like IEC 60601-1 dictate the baseline electrical and optical safety parameters ensuring a device operates consistently within its intended therapeutic window without risking burns or eye damage. Hardware preparation determines whether the science reaches the cells.
The invisible variable: thermal management
LED junction temperature directly impacts wavelength drift. As an LED heats up during operation, its emitted wavelength lengthens, pushing it out of the therapeutic window discussed in the previous section. Proper heat sinking and active cooling are prerequisites for maintaining the spectral accuracy required for cytochrome c oxidase absorption over a standard 10-to-20-minute treatment session. A device that runs hot fails silently. Thermal control preserves the exact physics the biology requires.
Executing the dose: the step-by-step mechanics of light delivery

A properly executed light therapy session begins before the user feels any warmth. The device needs a brief warm-up period, allowing LEDs to reach a stable operating temperature to prevent initial wavelength drift. Once stable, the chronological process relies on calculating cumulative dose. Fluence, measured in J/cm², is the product of irradiance (mW/cm²) multiplied by time in seconds. Research in the Journal of Biophotonics confirms that practitioners and users must calculate total energy delivered rather than turning on a light and guessing.
REDDOT LED supplied FDA-cleared, multi-wavelength panels with customized mounting brackets to a boutique California sports recovery studio facing long treatment times. Because the panels were engineered for high-irradiance output, the studio reduced client treatment times by 50% without compromising safety or efficacy. Hardware execution directly alters clinical workflow.
Physical geometry governs this execution. The inverse square law applies strictly to light therapy. Moving a panel just two inches further away can halve the irradiance reaching the skin, completely invalidating the calculated dose. Precision in placement matches precision in manufacturing.
Common belief: Any red light held near the body delivers a therapeutic dose.
What is actually true: Dose is a mathematical product of verified irradiance, exact distance, and timed exposure. Without controlling all three variables, the biphasic dose response curve guarantees suboptimal or inhibitory results. Knowing how does light therapy actually work means respecting the math.
Adapting the process for different form factors
Full-body high-irradiance panels operate under vastly different physics than localized, low-power devices. Facial masks position LEDs millimeters from the skin, requiring careful power calibrations to avoid exceeding the biphasic dose threshold. The SD-008 Shaping Mask uses 690 beads divided equally among 660nm-665nm Red, 450nm-480nm Blue, and 405-410nm Pink wavelengths across a 25.4×20.32×11.9 cm surface. This dense arrangement demands lower individual diode power compared to a wall-mounted panel to keep fluence within safe limits. Form factor dictates the entire dosing strategy.
Verifying the output: how to know the science is actually happening

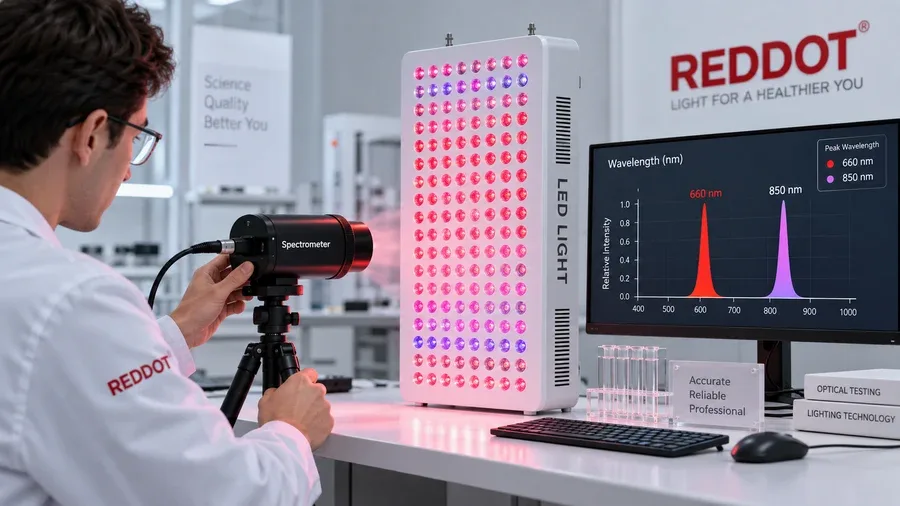
A legitimate therapeutic device will show sharp, narrow peaks exactly at 660nm and 850nm on a spectrometer graph. Biological results take weeks to manifest. Verifying the engineering output remains the only immediate way to confirm a device is working as intended. Spectrometers measure wavelength accuracy, while solar power meters calibrated for specific wavelengths measure irradiance. Cheap alternatives often display wide, sloppy bell curves on these graphs, indicating mixed LED bins that dilute the therapeutic effect.
Manufacturing certifications act as a proxy for verifiable quality. ISO 13485 certification requires documented quality management systems for medical devices. REDDOT LED operates a 10,000 m² R&D base with a 17-member team specializing in optics, electronics, and firmware, backed by over 70 granted patents. Every shipped device undergoes rigorous aging tests to verify output consistency before leaving the factory.
How do you know if light therapy is working? You can verify light therapy is working by measuring the device’s output with a spectrometer to ensure precise wavelength peaks (e.g., exactly 660nm and 850nm) and using a power meter to confirm adequate irradiance (mW/cm²) at your treatment distance, ensuring the total fluence falls within the established therapeutic window. Buyers should demand exact wavelength tolerance (±5nm), guaranteed irradiance at a specified distance, and proof of compliance with IEC 60601-1. Verification replaces faith with physics.
The no-BS reality: common failure points and why cheap devices fail

Any device glowing red does not automatically provide health benefits. Without optical engineering, a device is merely a colored lamp. The most pervasive failure point is “wavelength blending,” where manufacturers use cheaper, off-spectrum LEDs to save costs. The resulting light looks right to the human eye but fails to trigger cytochrome c oxidase. Irradiance exaggeration compounds this problem. Many consumer brands measure irradiance directly against the LED lens at distance zero to publish inflated numbers, whereas clinical standards require measurement at the actual treatment distance, such as 6 or 12 inches. This deception leads to severe under-dosing.
Thermal failure destroys devices over time. Units lacking proper aluminum heat sinks or active fans suffer rapid lumen depreciation and wavelength drift within minutes of operation. Over months, thermal stress permanently degrades the LED chips. A device that worked marginally well on day one becomes biologically inert by month six. Much public confusion stems from affiliate-driven content ignoring optical physics. Readers should seek peer-reviewed literature like WALT guidelines and manufacturer white papers grounded in ISO-certified testing. Marketing claims mean nothing without verifiable engineering.
Troubleshooting a stalled treatment protocol
If a clinic sees no results after several weeks, the protocol requires systematic troubleshooting. First, verify the distance and recalculate fluence using the inverse square law. Second, check if the device has overheating cut-offs interrupting the session prematurely. Third, request spectral data from the manufacturer to confirm the LEDs haven’t degraded past their therapeutic thresholds. An Australian retailer expanding its health tech category faced similar risks of non-compliant inventory; verifying full TGA and SAA documentation upfront prevented customs failures and ensured the hardware met safety baselines. Stalled results usually trace back to unverified hardware rather than flawed biology.
Key Takeaways
Light therapy works when photons at 660 nm or 850 nm are absorbed by cytochrome c oxidase in the mitochondria, triggering a photochemical reaction that increases ATP production. Because this mechanism depends on light reaching target tissue at a sufficient intensity, verifying a device’s irradiance output and wavelength accuracy matters far more than counting LEDs on a panel. Understanding these cellular mechanics helps separate verified photobiomodulation science from marketing claims.
Frequently Asked Questions
How does light therapy actually work on a cellular level?
Light therapy works on a cellular level through a photochemical reaction where specific wavelengths of light are absorbed by cytochrome c oxidase, an enzyme located inside the mitochondria. This absorption stimulates the electron transport chain, leading to increased adenosine triphosphate (ATP) production. Peer-reviewed research published in journals indexed on PubMed confirms that this boost in cellular energy supports tissue repair and reduces oxidative stress. The process relies entirely on photon absorption rather than heat generation.
What is the difference between red light and near-infrared light therapy?
Red light operates at wavelengths around 630 nm to 670 nm, while near-infrared (NIR) light uses longer wavelengths typically between 810 nm and 860 nm. The primary difference lies in penetration depth: red light absorbs primarily in the epidermis and dermis, making it suitable for skin-level applications, whereas NIR light penetrates deeper into muscle and joint tissue. Devices often combine both, such as panels engineered with a 660 nm to 850 nm ratio, to address multiple tissue depths simultaneously. Published optical physics standards confirm that longer wavelengths scatter less in biological tissue, allowing deeper reach.
How long does it take for light therapy to show results?
The timeline for visible or measurable results depends heavily on the condition being addressed and the irradiance delivered to the tissue. Acute issues like minor muscle fatigue may respond within days of consistent sessions, while chronic conditions involving deep tissue or systemic inflammation typically require several weeks of regular use. Clinical dosimetry guidelines emphasize that total energy dose, measured in joules per square centimeter (J/cm²), dictates the biological response over time. Consistency in session length and distance from the light source determines whether the cumulative dose reaches the therapeutic threshold.
Can you get burned from red light therapy?
Red light therapy devices do not emit ultraviolet (UV) radiation, which is the spectrum responsible for sunburns and DNA damage in skin cells. Photobiomodulation relies on non-ionizing visible and near-infrared light that produces a photochemical effect without burning tissue. However, low-quality devices with poor thermal management can generate excessive surface heat from their electronic components, which could cause discomfort or mild thermal injury if pressed directly against the skin. Safety standards like IEC 60601-1 exist specifically to regulate electrical and thermal safety limits in medical-grade equipment.
Does the wattage of a light therapy device matter?
Total electrical wattage indicates how much power a device consumes, but it does not directly tell you how much therapeutic light reaches your body. Irradiance, measured in milliwatts per square centimeter (mW/cm²) at a specific distance, is the metric that determines clinical effectiveness. A device drawing high wattage but using inefficient optics or poor LED binning will deliver less usable light to the tissue than a lower-wattage unit with precise lens engineering. Buyers evaluating equipment should always request third-party irradiance maps rather than relying on total wattage claims.
Is light therapy scientifically proven?
Photobiomodulation is supported by thousands of peer-reviewed studies documenting its effects on mitochondrial function, wound healing, and inflammation reduction. Regulatory bodies recognize these mechanisms; for example, the FDA clears specific light therapy devices for indications like pain relief and temporary increase in local blood circulation. The scientific consensus acknowledges that efficacy depends on delivering the correct wavelength, dose, and treatment protocol. Vague marketing claims often outpace the actual data, so verifying a manufacturer’s regulatory clearances and published test reports remains the most reliable way to assess a product’s scientific backing.
References & Sources
- U.S. Food and Drug Administration (FDA). “Medical Devices.” 2024.
- International Electrotechnical Commission (IEC). “IEC 60601-1 Medical Electrical Equipment Safety Standards.” 2024.
- National Institutes of Health (NIH). “Photobiomodulation and Light Therapy Research via PubMed.” 2024.
- International Organization for Standardization (ISO). “ISO 13485 Medical Device Quality Management Systems.” 2024.
- Hamblin, M.R. “Mechanisms and applications of the anti-inflammatory effects of photobiomodulation.” AIMS Biophysics, 2017.