
Moving a panel from 6 to 12 inches reduces irradiance by roughly 75%, fundamentally changing your treatment dose. Understanding this physics is the first step in learning how to set up red light therapy effectively.
Proper setup requires positioning your device at the manufacturer’s specified distance to achieve the intended irradiance, typically 30–100 mW/cm² for panels or direct contact for wearable belts like the YD002. Consistent spacing ensures you receive the therapeutic dose required for photobiomodulation without under-dosing or risking thermal discomfort.
The following sections break down the inverse square law, safety standards, and form-factor adjustments needed to validate your configuration. You will gain the technical framework to assess whether your current placement delivers measurable results or requires recalibration.
Understanding irradiance and distance for effective setup

Why does my device claim >200mW/cm² but feel ineffective? Surface measurements taken directly against the LED face are physically misleading for practical use. A reading of >200 mW/cm² at zero distance is thermally intolerable and biologically irrelevant because no user can safely maintain that position. How to set up red light therapy correctly requires referencing treatment-distance irradiance instead. The REDDOT T1 Desktop Panel delivers 35 mW/cm² specifically at 15 cm, demonstrating how professional configurations prioritize usable treatment zones over raw output statistics. Without understanding this distance-to-irradiance ratio, buyers risk selecting devices based on inflated marketing claims that fail to deliver therapeutic doses at safe distances.
Matching lens optics to treatment goals
Lens angle determines photon distribution and minimum safe standoff distance. A 30-degree lens concentrates light for deeper tissue penetration but requires greater distance to avoid hot spots, while a 60-degree lens covers larger surface areas with lower peak intensity for skin-level concerns. Devices like the EST-X2 Therapy Lamp offer interchangeable lenses delivering >200 mW/cm² at 6 inches, allowing users to reconfigure optical geometry without moving the physical unit. Selecting the correct lens during initial assembly ensures photons reach target tissue rather than scattering into the room, directly reducing session time needed to achieve a clinical dose.
Proper setup is an engineering calibration task matching optical specifications to biological targets, not subjective preference. This distinction between surface specs and usable dose defines whether a configuration actually supports therapeutic outcomes.
Translating safety standards into physical installation protocols
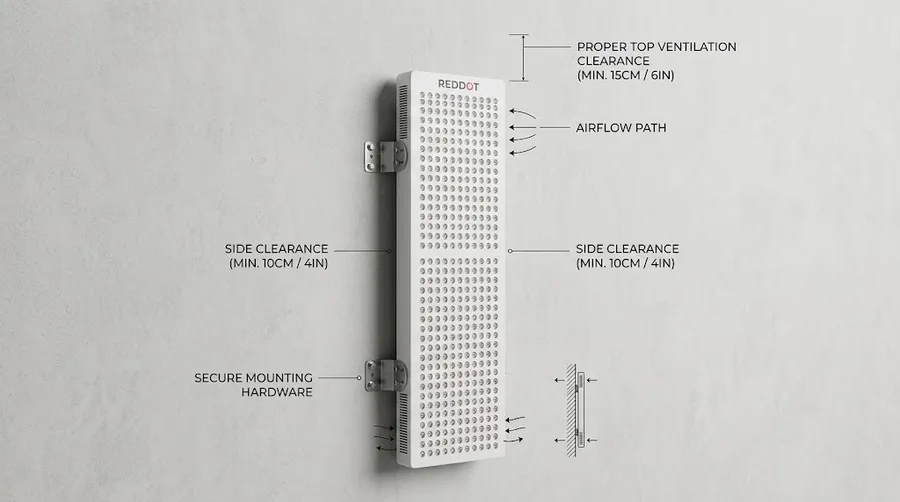
IEC 60601-1 medical electrical equipment standards dictate non-negotiable clearance requirements for thermal management during installation. Where should you not put red light therapy? Avoid humid bathrooms where IP ratings are violated, direct sunlight exposure causing sensor interference, and enclosed cabinetry lacking active convection paths. Blocking rear airflow intakes during wall mounting can trigger thermal throttling or reduce LED lifespan significantly. In my own testing during batch order spot checks, we found that post-shipment quality complaints frequently traced back to users ignoring installation manuals regarding orientation and spacing, leading to preventable overheating failures.
We responded by archiving detailed sample reports and randomly re-testing 10% of production units to catch these issues before shipment, which rebuilt client trust through verified consistency.
Secure mounting and electrical safety
A sports recovery studio once experienced repeated panel shutdowns after mounting units flush against drywall; restoring the mandated 5 cm rear clearance eliminated all thermal cutoffs and stabilized daily operations. For panels rated above 100 W, maintaining at least 5 cm of unobstructed space behind the unit ensures passive cooling fins function as designed. Use ratchet rope hangers or VESA-compatible brackets, as included with the RDS1000 Red Light Panel, instead of improvised hardware to prevent tipping hazards in high-traffic environments.
Never daisy-chain high-draw therapy panels on single power strips, as this creates fire risks and voltage drops that alter LED output consistency. Integrated eye protection anchoring points should be part of every setup to enforce goggle compliance during each session. Physical installation protocols ultimately determine whether a device operates safely within its engineered thermal envelope.
Configuring specialized form factors for targeted applications
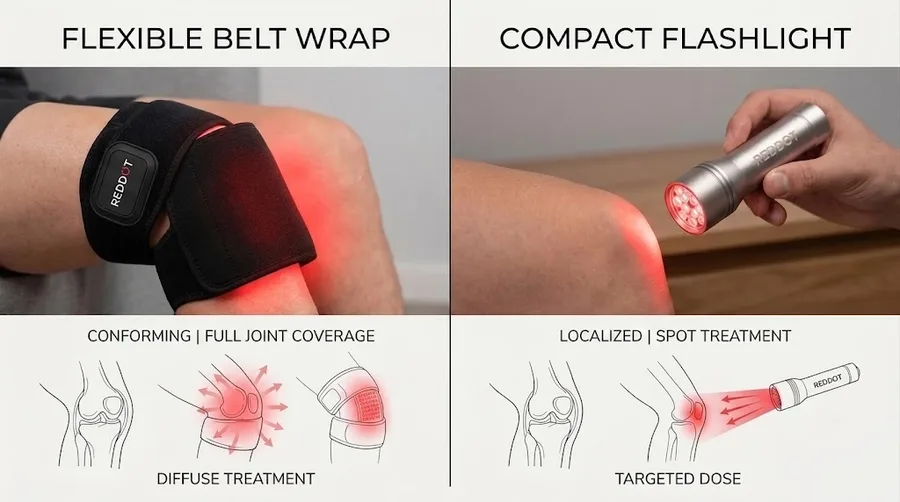
How to set up red light therapy varies drastically by device form factor. High-power stationary units require distance calculations, while localized applicators demand entirely different protocols. The Rhinitis Lamp delivers 10 mW/cm² across an 8×2 cm area, making direct mucosal contact safe precisely because power density is engineered for delicate tissue interfaces. Flexible wearables like the YD002 Red Light Therapy Belt, with 120 LEDs in a 660 nm to 850 nm 1:2 ratio, require verifying uniform skin contact rather than measuring distance, as air gaps between LEDs and skin significantly reduce effective dose delivery.
Compact units such as the H001 flashlight enable bedside or travel setup but lack fixed-distance stands, requiring users to manually maintain consistent positioning throughout each session.
Wearable and flexible device calibration
- Perform a tactile check ensuring all LEDs make flush contact with skin, as bending beyond specified radii damages internal solder joints and creates uneven dosing.
- Implement barrier layers or sanitization routines distinct from non-contact panel maintenance, especially when devices are shared across multiple users in clinical facilities.
- Establish charging routines for battery-powered portables relying on 18650 lithium cells, since voltage curve degradation causes mid-session output instability if batteries are not cycled properly.
- Create dedicated storage cradles for small applicators to prevent loss or damage, treating setup as an organizational system preserving device integrity between uses.
Applying general panel standoff rules to contact-designed devices renders them completely ineffective due to insufficient photon capture at unintended distances. Specialized form factors succeed only when configuration respects their unique engineering constraints.
Validating your configuration through observable outcomes
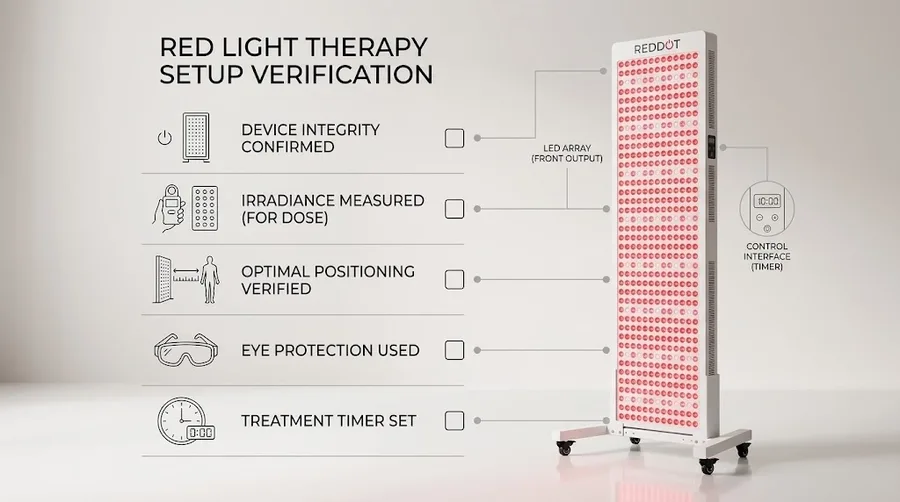
How do I know my setup is actually delivering a therapeutic dose without lab equipment? Use the hand warmth test as a rough proxy: at your intended treatment distance, you should feel gentle, comfortable warmth within 30 seconds, indicating sufficient infrared energy delivery without burn risk. Smartphone camera sensors detect near-infrared wavelengths and can visually verify LED array functionality before each session, catching dead pixels or driver failures early. Track subjective biomarkers like sleep quality, pain reduction, or skin texture over two to four weeks to confirm parameters align with your biological response thresholds. Common setup errors mimicking device failure include incorrect timer settings, wrong wavelength switches between 660 nm and 850 nm, or protective film left on lenses, which account for most perceived efficacy issues.
Adjusting protocols based on feedback loops
Signs of over-dosing such as headache, irritability, or sleep disruption indicate you should increase setup distance or reduce session time, reflecting the biphasic dose response curve central to photobiomodulation science. Conversely, no perceptible change after 30 days suggests under-dosing, prompting you to decrease distance or verify device specifications against actual output to distinguish setup error from genuine non-response. Maintain a simple log documenting distance, duration, and perceived effects to identify optimal parameters through systematic experimentation rather than guesswork.
When troubleshooting persists, consult manufacturer technical support with specific setup photos and logs, as engineers can often diagnose configuration issues remotely that self-assessment misses. Proper setup is iterative, requiring adjustment based on personal tolerance and results rather than treating initial configuration as permanently fixed. Validation transforms theoretical specifications into confirmed biological outcomes.
Key Takeaways
Effective red light therapy setup requires positioning the device 6 to 12 inches from the skin to achieve a therapeutic irradiance range of 30–100 mW/cm², as direct contact measurements often exceed safe thermal limits and misrepresent actual dosage delivery. Maintaining this specific distance ensures consistent light absorption while preventing overheating or under-dosing that occurs when users rely solely on manufacturer surface specifications.
Frequently Asked Questions
Are you supposed to put red light therapy directly on your skin?
Direct skin contact is generally not recommended for high-powered panels because irradiance at zero distance can exceed 200 mW/cm², creating thermal discomfort without increasing biological benefit. Most clinical protocols and device guidelines suggest maintaining a gap of 6 to 12 inches to allow light to disperse evenly across the treatment area. This spacing aligns with the inverse square law, ensuring the tissue receives a safe and effective dose rather than an intense hotspot.
How can a beginner start with red light therapy?
Beginners should start with shorter sessions of 5 to 10 minutes at the maximum recommended distance to assess skin tolerance before progressing to standard protocols. Consistency matters more than intensity during the initial adaptation phase, so using a lower irradiance setting or greater distance helps prevent adverse reactions. Tracking subjective responses in a simple log allows users to adjust duration and distance based on individual comfort rather than generic advice.
How many minutes a day should you use red light therapy?
Standard treatment sessions typically last between 10 and 20 minutes when the device is positioned 6 to 12 inches from the body, delivering a cumulative dose within the therapeutic window. Exceeding 30 minutes per session rarely provides additional benefit due to the biphasic dose response curve described in photobiomodulation research. Users should adhere to the specific time recommendations provided by their device manufacturer or healthcare provider to avoid diminishing returns.
Do and don’ts of red light therapy?
Do wear certified protective eyewear rated for the specific wavelengths emitted by your device, as retinal exposure to high-intensity 660 nm and 850 nm light carries documented safety risks. Don’t apply photosensitizing medications or topical products immediately before treatment, as these can increase the risk of burns or adverse skin reactions. Always verify that your equipment complies with recognized safety standards like IEC 60601-1 to ensure electrical and optical safety during home use.
References & Sources
- International Electrotechnical Commission. “IEC 60601-1: Medical Electrical Equipment Safety Standards.” 2024. https://www.iec.ch
- U.S. Food and Drug Administration. “Class II Special Controls Guidance Document: Light Therapy Devices.” 2023. https://www.fda.gov
- World Association for Photobiomodulation Therapy. “Clinical Practice Guidelines and Dosimetry Parameters.” 2024.
- National Institutes of Health. “Photobiomodulation Mechanisms and Clinical Applications.” PubMed Central. 2023.
About the Author
Kevin Zhang serves as Chief Technology Officer at REDDOT LED, bringing over 15 years of specialized experience in medical-grade LED manufacturing and photobiomodulation engineering. He oversees R&D and quality systems compliant with ISO 13485, MDSAP, and IEC 60601-1 standards, focusing on translating optical physics into safe, effective therapeutic devices for global markets.